- 22 岁男性:反复非创伤性「蛛网膜下腔出血」样表现与癫痫持续状态;术中见脑表柏油样黑色外观。
- 弥漫软脑膜富色素上皮样黑色素细胞增生,Melan-A+、核 BAP1 保留;NGS:NRAS Q61H + EIF1AX G8R。
- 组织学介于 CNS-WHO 软脑膜黑色素细胞增生症与黑色素瘤病之间的交界性原发弥漫性软脑膜黑色素细胞肿瘤(PLMN)。
虚拟玻片
数字玻片(Box 1):https://isn-slidearchive.org/?col=ISN&fol=Archive&file=20260528.svs
临床病史与影像
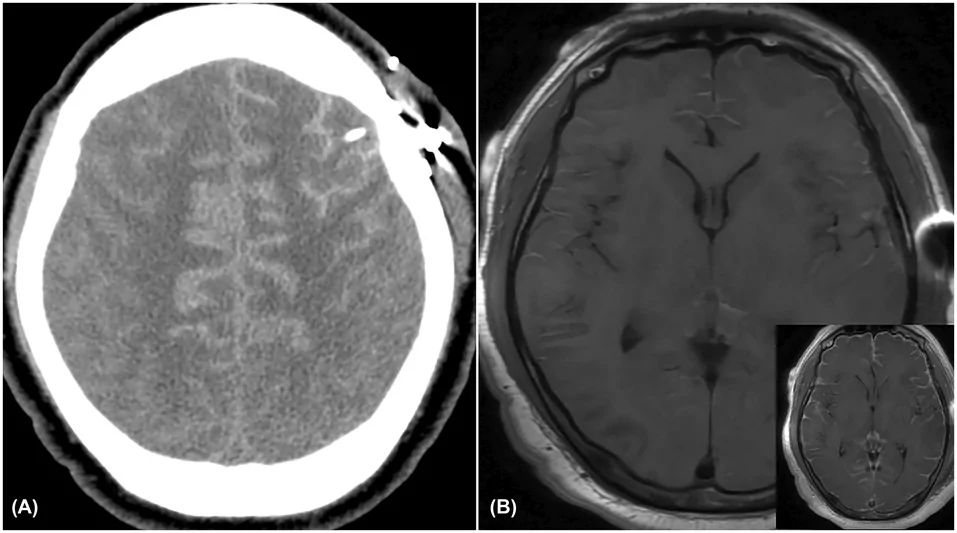
本例为 22 岁男性,既往有高血压;因多次非创伤性蛛网膜下腔出血及癫痫持续状态自外院转入。初始非增强 CT 显示以双侧额叶为主的脑沟密度增高,拟似蛛网膜下腔出血(图 1A)。随后脑 MRI 显示双侧大脑脑沟固有 T1 高信号,并沿脑沟、脑干表面、颅神经及脑室缘叠加弥漫软脑膜强化(图 1B)。遂行左额开颅活检以明确诊断。术中打开硬膜后,可见脑表面呈深色、柏油样外观。获取病变组织送病理检查。
病理所见
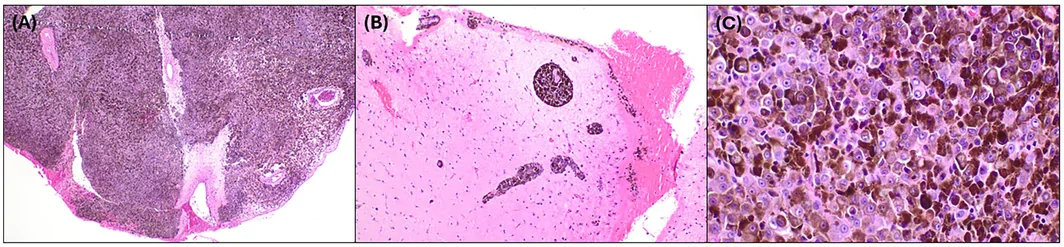
H&E 切片显示弥漫软脑膜增生:高度色素沉着的上皮样黑色素细胞,核异型中–重度,核分裂少见(图 2A、C;Box 1)。未见坏死。可见沿 Virchow-Robin 间隙延伸,但无明确脑实质侵犯(图 2B)。免疫组化:肿瘤细胞 Melan-A 阳性,核 BAP1 表达保留。临床上患者无皮肤黑色素瘤病史,亦无神经皮肤综合征。
二代测序检出激活型 NRAS p.Gln61His(Q61H)突变及外显子 1 热点 EIF1AX p.Gly8Arg 突变。全基因组甲基化分析综合结果为「No Match」。相应拷贝数图示 8 号染色体浅获得,以及 9q 与 11q(局灶)浅缺失;9p21(CDKN2A/B)与 3p 似完整。
鉴于影像上为弥漫软脑膜过程,并按中枢神经系统世界卫生组织(CNS-WHO)框架:弥漫性原发软脑膜黑色素细胞肿瘤(PLMN)依据异型、核分裂活性、侵犯与坏死,分为黑色素细胞增生症(良性)或黑色素瘤病(恶性)。本例显示核异型,已超出经典型软脑膜黑色素细胞增生症所预期的细胞学温和程度;但核分裂低、无坏死,又未达显性黑色素瘤病。组织学上,本例落在黑色素细胞增生症与黑色素瘤病之间的交界区。
综合临床病史、放射学、肿瘤形态与分子结果,更符合 PLMN,而非常规转移性皮肤黑色素瘤。总体支持交界性弥漫性软脑膜黑色素细胞肿瘤、NRAS 与 EIF1AX 突变,并具潜在侵袭行为。
最终诊断
原发性弥漫性软脑膜黑色素细胞肿瘤,NRAS 与 EIF1AX 突变,介于黑色素细胞增生症与黑色素瘤病之间。
讨论
累及 CNS 的原发性黑色素细胞肿瘤构成极为罕见的谱系,可归为恶性或良性。临床表现可为局灶性边界清楚的病变,或沿软脑膜广泛受累的弥漫性病变。按最新 2021 CNS-WHO 肿瘤分类,软脑膜黑色素细胞增生症为细胞学温和的黑色素细胞弥漫或多灶性脑膜增生;软脑膜黑色素瘤病则为常可侵犯 CNS 实质的黑色素细胞弥漫或多灶性脑膜增生。二者均起源于源自神经嵴的固有软脑膜黑色素细胞。
从流行病学看,弥漫性软脑膜黑色素细胞肿瘤极为罕见,人群研究难以评估。成人与儿童均可发生。黑色素细胞增生症主要见于神经皮肤黑色素沉着症(NCM)背景下的儿童。黑色素瘤病常呈双峰年龄分布,可出现于伴或不伴 NCM 的儿童,以及以 40 岁左右为主的成人。
Kinsler 等提出,软脑膜黑色素瘤病与黑色素细胞增生症的发病机制主要与 NRAS 基因密码子 61 的合子后突变相关,通过原癌基因激活造成初始遗传学打击,使 NRAS 在多步骤致瘤过程中充当主要驱动。NRAS 是 RAS GTPase 家族重要成员,主要通过 RAF/MEK/ERK 与 PI3K/mTOR 通路调控细胞增殖、分化与存活。
本例尚检出外显子 1 的 EIF1AX p.Gly8Arg 突变。据 Küsters-Vandevelde 等,涉及 EIF1AX(外显子 1、2 及侧翼内含子区)的错义突变在 PLMN 中频率相对较高(约 21%),且常与 GNAQ、GNA11、NRAS 突变共现,提示 EIF1AX 突变出现于致瘤通路较后阶段。
本例展示了一种罕见肿瘤:组织学上在黑色素细胞增生症与黑色素瘤病之间显著重叠,无法归入任一类别,成为罕见的交界性弥漫性软脑膜黑色素细胞肿瘤(NRAS 与 EIF1AX 突变),并具潜在侵袭行为。
Virtual glass slide
Box 1. Access at https://isn-slidearchive.org/?col=ISN&fol=Archive&file=20260528.svs.
Clinical history and imaging
This case involves a 22-year-old male with a past medical history significant for hypertension, who was transferred from an outside hospital on investigation of multiple prior nontraumatic subarachnoid hemorrhages and status epilepticus. Initial non-contrast computed tomography (CT) revealed increased sulcal density primarily in the bilateral frontal lobes mimicking a subarachnoid hemorrhage (Figure 1A). Subsequent brain magnetic resonance imaging (MRI) revealed T1 intrinsic hyperintensity of the bilateral cerebral sulci with diffuse superimposed leptomeningeal enhancement along the sulci, surface of the brainstem, cranial nerves, and ventricular margins (Figure 1B). A left frontal craniotomy was pursued for biopsy and definitive diagnosis. Intraoperatively, after the dura was opened, a dark, tar-like appearance involving the surface of the brain was visualized. Lesional tissue was obtained and sent for pathological analysis.
Findings
Histological analysis of the H&E-stained sections demonstrated a diffuse leptomeningeal proliferation of highly pigmented epithelioid melanocytic cells with moderate to severe nuclear atypia and infrequent mitotic figures (Figure 2A,C, Box 1). Necrosis was absent. Extension into the Virchow-Robin spaces without definitive parenchymal invasion was noted (Figure 2B). Immunohistochemistry staining revealed the tumor cells to be positive for Melan-A with preserved nuclear BAP1 expression. Clinically, the patient did not have a history of cutaneous melanoma or neurocutaneous syndrome.
Next-generation sequencing revealed an activating NRAS p.Gln61His (Q61H) mutation and a hotspot EIF1AX p.Gly8Arg mutation in exon 1. Whole genome methylation profiling was performed with a composite methylation profile listed as “No Match.” The corresponding copy number plot revealed a shallow gain of chromosome 8 and shallow deletions of 9q and 11q (focal), while 9p21 (CDKN2A/B) and 3p appeared intact.
Given the concerning imaging findings of a diffuse leptomeningeal process, and by applying the Central Nervous System-World Health Organization (CNS-WHO) framework, diffuse primary leptomeningeal melanocytic neoplasms (PLMNs) are classified as melanocytosis (benign) or melanomatosis (malignant) based on atypia, mitotic activity, invasion, and necrosis. In this case, the lesion displayed nuclear atypia and exceeded the cytologic blandness expected for classic meningeal melanocytosis. However, the low mitotic activity and lack of necrosis made the lesion fall short of overt melanomatosis. Histologically, this placed the lesion within a borderline zone between melanocytosis and melanomatosis.
The combination of clinical history, radiological findings, tumor morphology, and molecular findings was determined to be more consistent with a PLMN than with a conventional metastatic cutaneous melanoma. Overall, the findings support a borderline diffuse leptomeningeal melanocytic neoplasm, NRAS- and EIF1AX-mutant, with potential for aggressive behavior.
Final diagnosis
Primary diffuse leptomeningeal melanocytic neoplasm, NRAS and EIF1AX-mutant, borderline between melanocytosis and melanomatosis.
Discussion
Primary melanocytic tumors involving the CNS represent a spectrum of very rare tumors that can be classified as either malignant or benign. These tumors can present clinically as either a focally well-circumscribed lesion or a diffuse lesion with widespread involvement along the leptomeninges. As defined by the most recent 2021 CNS-WHO tumor classification system, meningeal melanocytosis is a diffuse or multifocal meningeal proliferation of cytologically bland melanocytic cells, while meningeal melanomatosis is a diffuse or multifocal meningeal proliferation of melanotic cells that often show invasion into the CNS parenchyma. Both entities arise from native leptomeningeal melanocytes derived from neural crest cells.
From an epidemiological standpoint, diffuse meningeal melanocytic neoplasms are very rare, making population-based studies challenging to assess and quantify. These tumors have been reported to occur in both adults and children. Melanocytosis primarily affects children in the setting of neurocutaneous melanosis (NCM). Melanomatosis often exhibits a bimodal age distribution and may manifest in children, with or without NCM, and in adults predominantly in the 4th decade of life.
It has been proposed, in a study by Kinsler et al., that the pathogenesis involving meningeal melanomatosis and melanocytosis is predominately associated with postzygotic mutations in the NRAS gene at codon 61, which results in an initial genetic insult via proto-oncogene activation where the NRAS gene acts as a primary driver in a multi-step oncogenic process. The NRAS gene is an important member of the RAS GTPase family that primarily regulates cellular proliferation, differentiation, and survival involving the RAF/MEK/ERK and PI3K/mTOR pathways.
The present case also showed an EIF1AX p.Gly8Arg mutation in exon 1. According to a study by Küsters-Vandevelde et al., detection of missense mutations involving EIF1AX (exon 1 and 2 and flanking intronic regions) was found to occur at a relatively high frequency (~21%) in PLMNs. These mutations were also observed generally co-occurring with GNAQ, GNA11, and NRAS mutations, suggesting that the EIF1AX mutations arise later in the tumorigenesis pathway.
This interesting case demonstrates a rare tumor with unique histological features where significant overlap was observed between melanocytosis and melanomatosis. The tumor could not be placed in either category, making it a rare borderline diffuse leptomeningeal melanocytic neoplasm, NRAS- and EIF1AX-mutant, with potential for aggressive behavior.