定义 / 概述
SWI/SNF 复合体缺失型鼻腔鼻窦癌包括发生于鼻腔鼻窦、伴 SMARCB1(INI1)或 SMARCA4(BRG1)蛋白表达缺失的低分化至未分化上皮性肿瘤(Adv Anat Pathol 2023;30:95;AJNR Am J Neuroradiol 2023;44:1116)。
要点
- 起源于鼻腔鼻窦。
- 定义性特征为 SMARCB1(INI1)或 SMARCA4(BRG1)蛋白表达缺失。
- 公认有 3 个亚型:SMARCB1 缺失型鼻腔鼻窦癌;SMARCB1 缺失型鼻腔鼻窦腺癌(必须至少局灶具有腺样或卵黄囊形态);SMARCA4 缺失型鼻腔鼻窦癌。
- 临床病程具有侵袭性。
术语
鼻腔鼻窦未分化癌(以往术语;目前不推荐使用)。
ICD 编码
- ICD-O:8044/3 — SWI/SNF 复合体缺失型鼻腔鼻窦癌。
- ICD-10:C30.0 — 鼻腔恶性肿瘤;C31.1 — 筛窦恶性肿瘤。
- ICD-11:2C20.Z & XH1YY4 — 鼻腔恶性肿瘤,未特指,及未分化癌,非特指型;2C22.2 & XH1YY4 — 副鼻窦恶性肿瘤,未特指,及未分化癌,非特指型。
流行病学
- 所有亚型均以男性多见。
- 年龄范围广,从青年成人到老年人均可发生(Am J Surg Pathol 2017;41:458;Head Neck Pathol 2022;16:168)。
部位
- SMARCA4 缺失型鼻腔鼻窦癌及 SMARCB1 缺失型鼻腔鼻窦腺癌:发生于鼻腔,累及多个鼻腔鼻窦部位(Head Neck Pathol 2022;16:168)。
- SMARCB1 缺失型鼻腔鼻窦癌:发生于鼻旁窦(主要为筛窦),可不同程度累及鼻腔(Am J Surg Pathol 2017;41:458)。
病理生理
- 开关 / 蔗糖非发酵(SWI/SNF)染色质重塑复合体发挥肿瘤抑制作用,由超过 20 个基因编码的蛋白组成。
- 可见多种突变,呈基因特异性聚集;与鼻腔鼻窦最相关的两个亚基改变为 SMARCB1 和 SMARCA4。
- SMARCB1 缺失源于染色体 22q11.2 的双等位基因缺失或失活。
- SMARCA4 缺失源于染色体 19p13.2 的双等位基因失活(Head Neck Pathol 2022;16:168)。
病因
不明。
临床特征
- 临床上可模拟良性疾病,仅有轻微鼻塞症状。
- 因肿块效应压迫脑神经及其分支而出现明显临床表现(Cancers 2022;14:3285)。
- 局部侵袭性强,常于 T4 期就诊,已侵犯眼眶和颅内。
诊断
- 理论上细胞学材料可能足以诊断,但需制作细胞块以进行相关免疫组织化学检查。
- 取材问题会使细胞学或组织学诊断困难(Head Neck Pathol 2022;16:168)。
- 诊断 SMARCB1 缺失型鼻腔鼻窦腺癌必须存在腺样或卵黄囊成分。
- 当有限的活检材料不能明确诊断时,切除标本可使形态评估更完整。
- WHO 组织学诊断标准:
- 必需:位于鼻腔鼻窦;未分化癌伴 SMARCB1(INI1)或 SMARCA4(BRG1)缺失,但不具有其他肿瘤实体的特征;腺癌亚型需有明确腺体形成或卵黄囊瘤样特征。
- 期望具备:存在横纹肌样细胞;腺癌变型具有卵黄囊样特征。
影像学描述
- 就诊时为 T4 期,累及多个鼻窦及邻近眼眶、颅内区域。
- 明显强化,T2 呈中等信号,中度弥散受限,氟脱氧葡萄糖(FDG)摄取增高。
- 解剖边界模糊,伴骨质改变。
- CT 所示钙化可能代表残留骨碎片,或侵袭性骨膜反应所形成的发束样外观。
- 参考文献:AJNR Am J Neuroradiol 2016;37:1925。
影像图(外部链接)
预后因素
- SMARCB1 缺失型鼻腔鼻窦癌:16 个月时死亡率为 56%(Am J Surg Pathol 2017;41:458);病变无法切除及转移是最常见死亡原因;T4 期及男性与较差预后相关。
- SMARCB1 缺失型鼻腔鼻窦腺癌:因随访资料有限,目前尚未明确。
- SMARCA4 缺失型鼻腔鼻窦癌:高度侵袭性,生物学行为与鼻腔鼻窦以外的同类肿瘤相似;约 67% 的患者在诊断后一年内死亡(Arch Pathol Lab Med 2022;146:1122)。
病例报告
- 53 岁男性,出现支气管内转移(Acta Cytol 2019;63:431)。
- 54 岁女性,持续左侧症状,包括鼻出血、偏侧头痛及眼部症状(Pathol Int 2022;72:53)。
- 58 岁男性,右侧鼻塞、嗅觉减退及右眼球突出(Diagn Pathol 2025;20:102)。
- 64 岁男性,右侧头痛加重及第六脑神经麻痹(Cureus 2025;17:e77217)。
- 72 岁男性,左侧面部疼痛及鼻阻塞,后出现肺转移(J Surg Case Rep 2021;2021:rjab161)。
治疗
- 多模式治疗:手术切除、化疗及放疗(Cancers 2022;14:3285)。
- 诱导化疗可降低远处转移风险;对诱导化疗反应良好与随后对放疗反应良好相关。
- 接受根治性放化疗的患者,其生存结局优于以手术切除为初始治疗者。
- 对诱导化疗反应不佳时,随后采用手术切除(J Clin Oncol 2019;37:504)。
- 针对 SWI/SNF 复合体缺失相关下游改变的靶向治疗正在研究中。
- SMARCB1 蛋白表达缺失后 EZH2 活性升高,使 EZH2 成为小分子抑制剂的治疗靶点(Cancers 2022;14:3285)。
大体描述
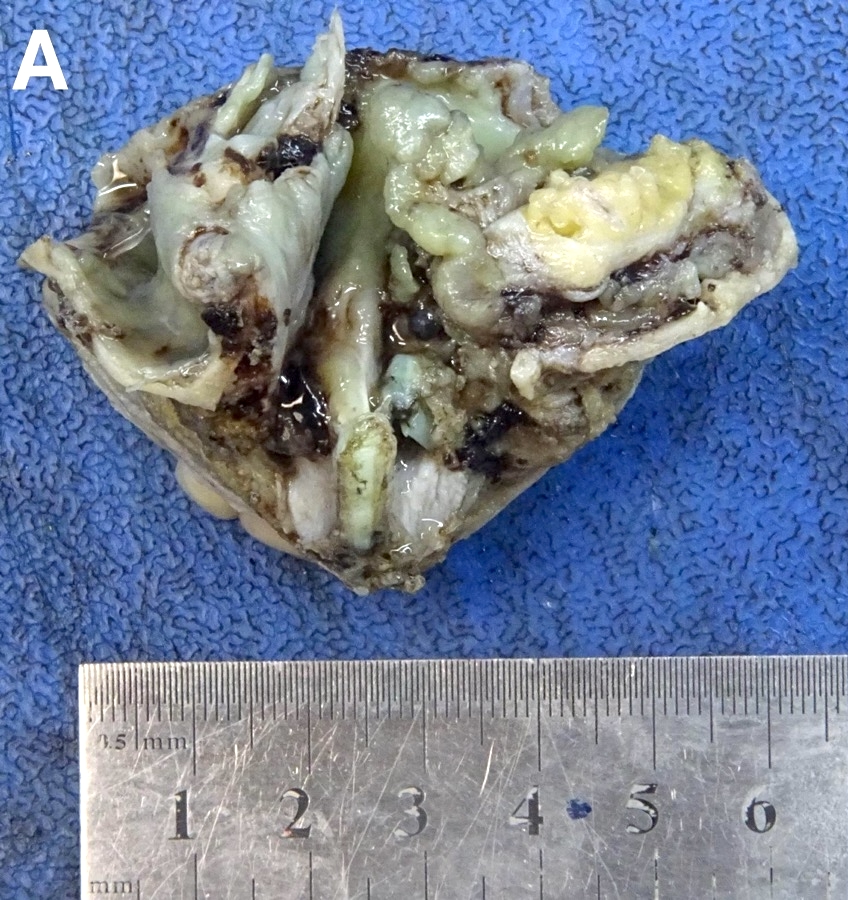
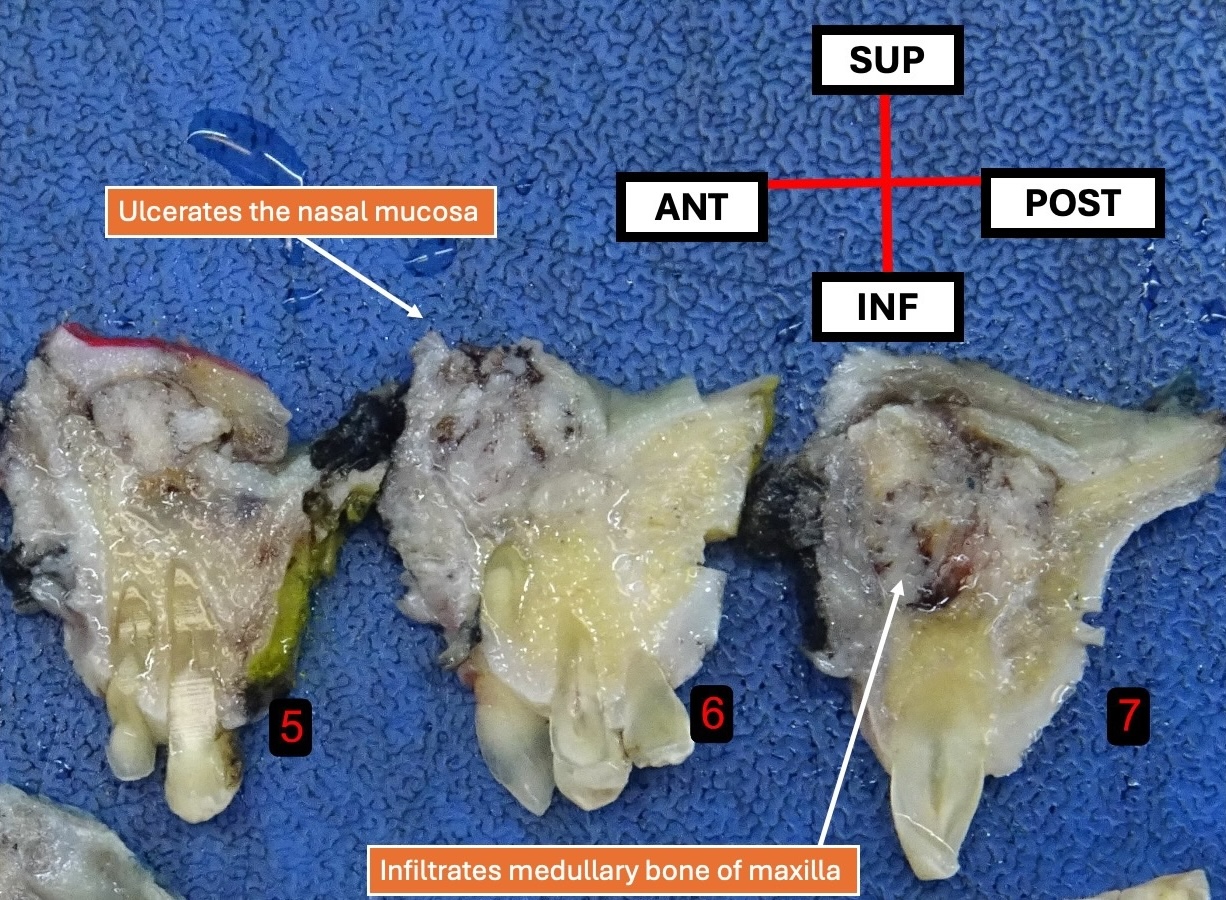
- 常表现为 T4 期病变,生长高度浸润,侵犯局部结构的骨质,如上颌骨(AJNR Am J Neuroradiol 2016;37:1925)。
- 表面可呈外生性乳头状(Am J Surg Pathol 2017;41:458)。
大体图像
冰冻切片描述
- 冰冻切片表现为未分化高级别恶性肿瘤。
- 在诊断已明确的情况下,可用于评估切缘状态。
镜下(组织学)描述
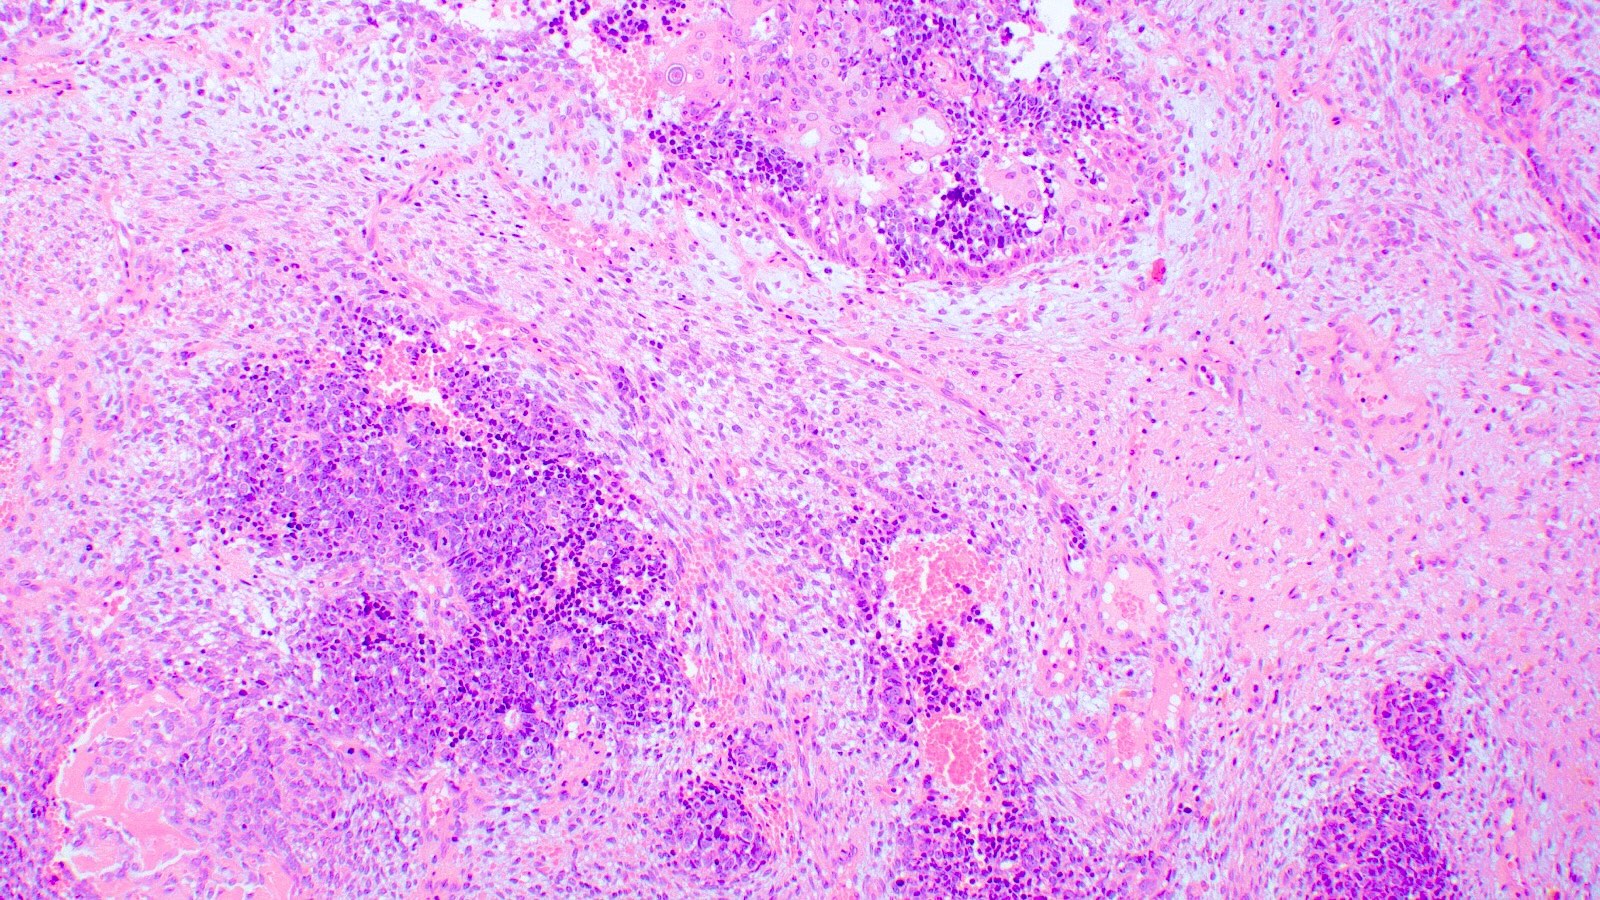
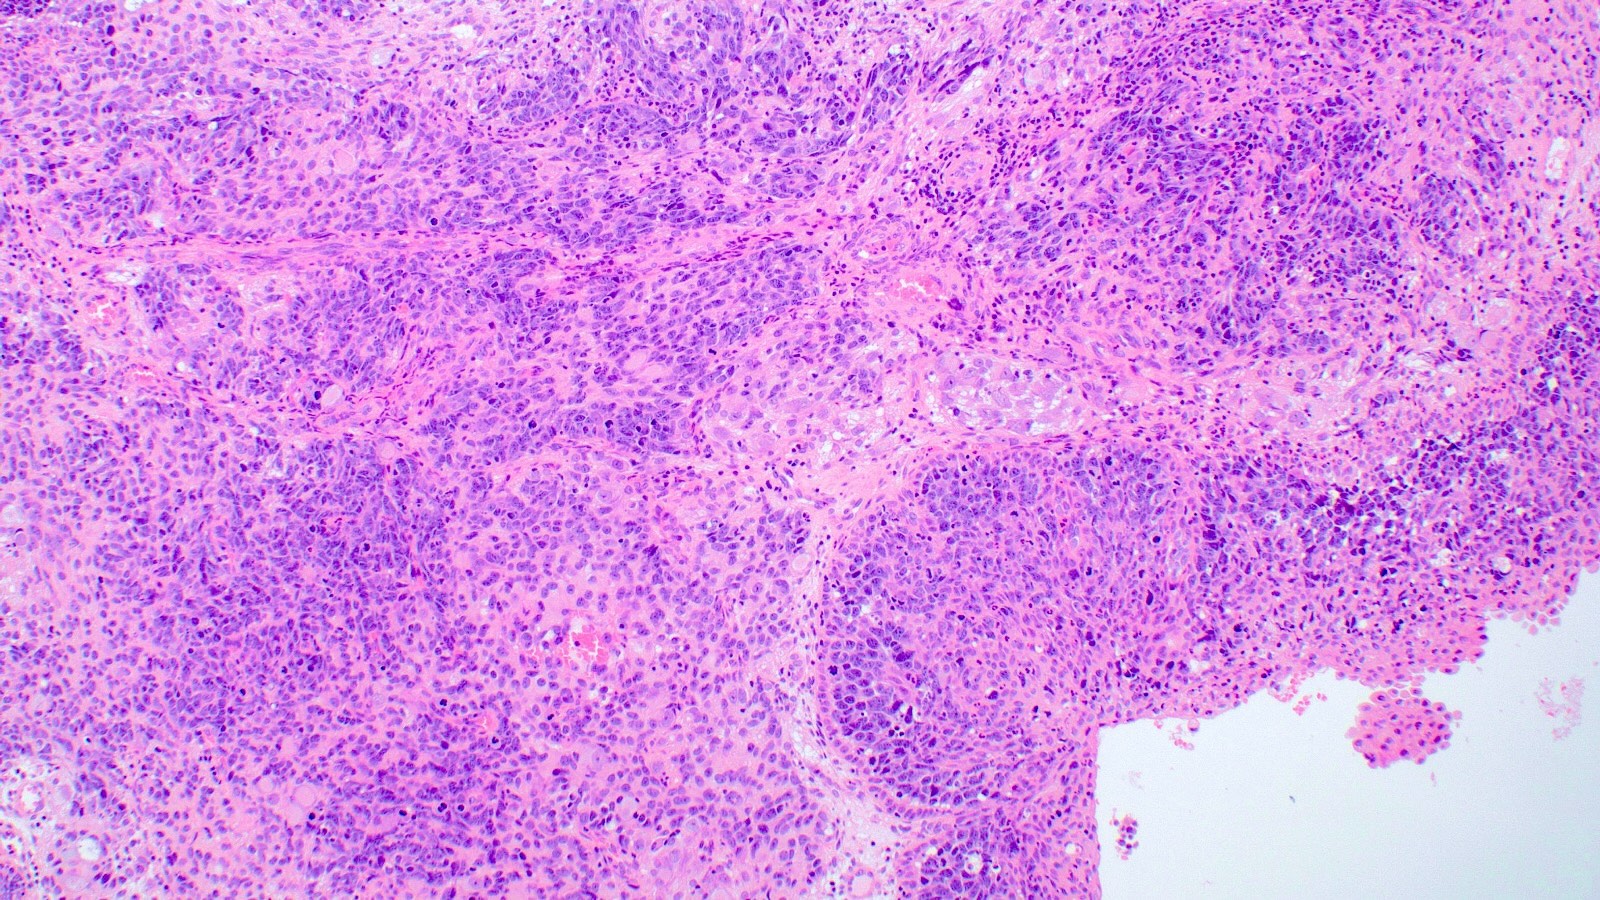
SMARCB1 缺失型鼻腔鼻窦癌(Head Neck Pathol 2022;16:168)
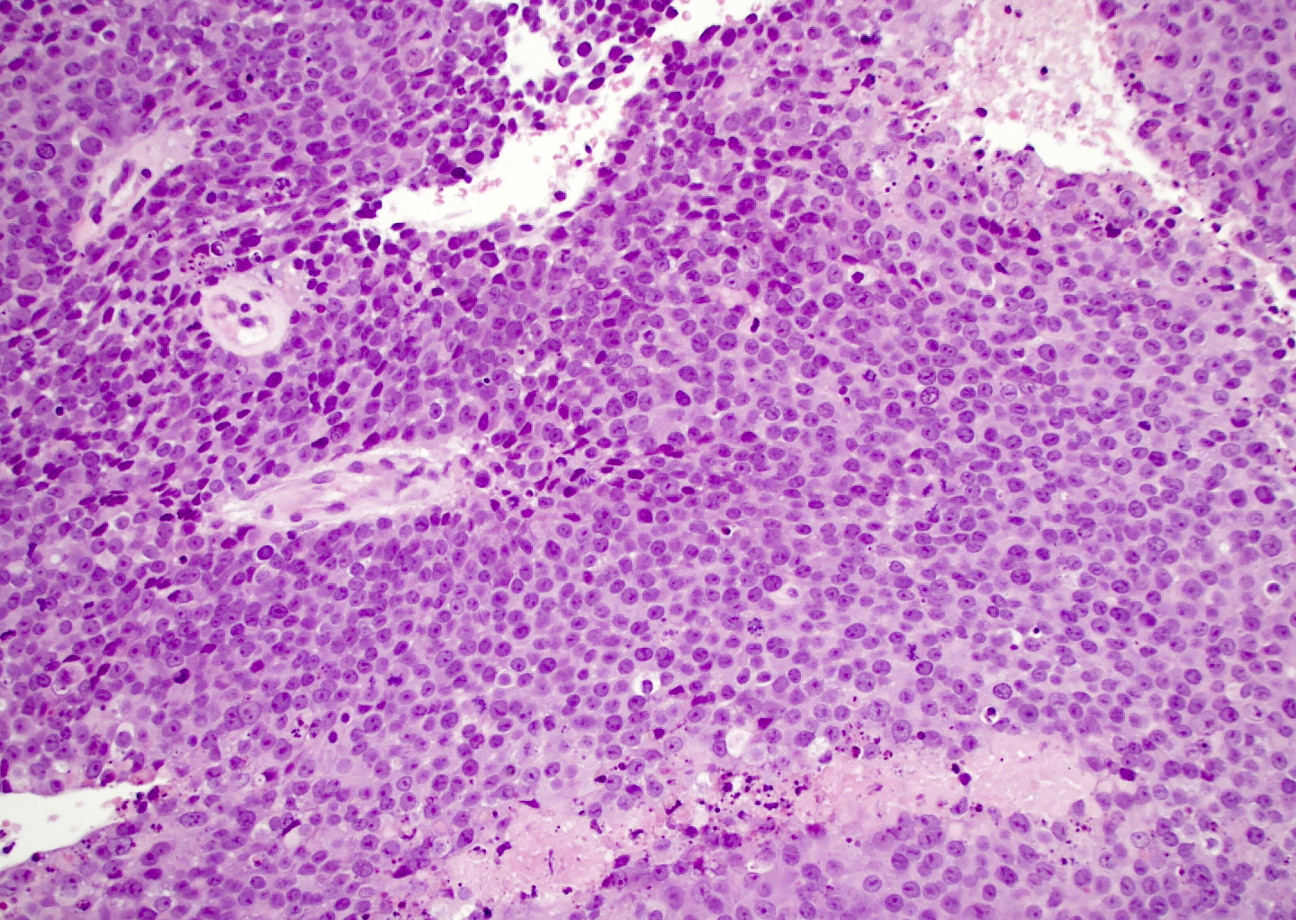
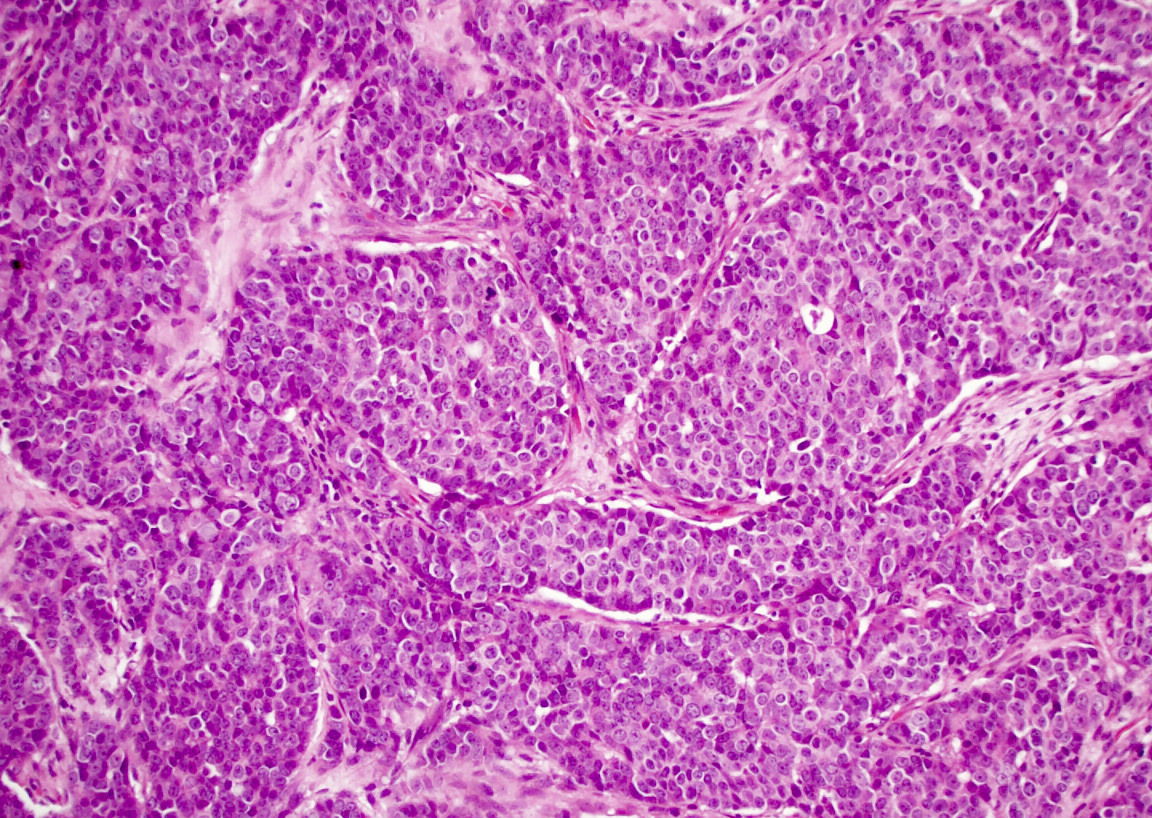
- 细胞形态单一,以基底样形态为主(60% 的病例)。
- 周边呈栅栏状排列,与基底样鳞状细胞癌(SCC)无法区分(Am J Surg Pathol 2017;41:458)。
- 呈嗜酸性、浆细胞样 / 横纹肌样形态(30% 的病例)(Am J Surg Pathol 2017;41:458)。
- 无鳞状分化,缺乏角化及常规鳞癌形态。
- 罕见透明细胞和梭形细胞。
- 可沿黏膜呈 Paget 样播散,模拟原位癌,但不应存在真正的表面上皮异型增生。
- 可呈乳头状生长并占据黏液腺,形成内翻性外观。
SMARCB1 缺失型鼻腔鼻窦腺癌(Head Neck Pathol 2020;14:465)
- 5%–100% 的肿瘤中可见明确腺体形成,表现为小管、筛状结构及腔内或细胞内腔隙。
- 偶呈卵黄囊样外观,即黏液样背景中的微囊状 / 网状结构。
- 以嗜酸细胞样 / 浆细胞样形态为主,伴黏液样间质。
- 高级别细胞学特征,包括核多形性、坏死及核分裂象。
- 罕呈梭形、鳞状或透明细胞样外观。
SMARCA4 缺失型鼻腔鼻窦癌(Head Neck Pathol 2022;16:168)
- 大片状排列的大型上皮样间变细胞。
- 可有不同程度的巢状及梁状结构。
- 缺乏腺样及鳞状分化。
- 核分裂活跃,坏死广泛。
- 罕见发育不全的神经内分泌样菊形团。
- 基底样及横纹肌样细胞通常只占少数,但这些特征也可占优势。
镜下(组织学)图像
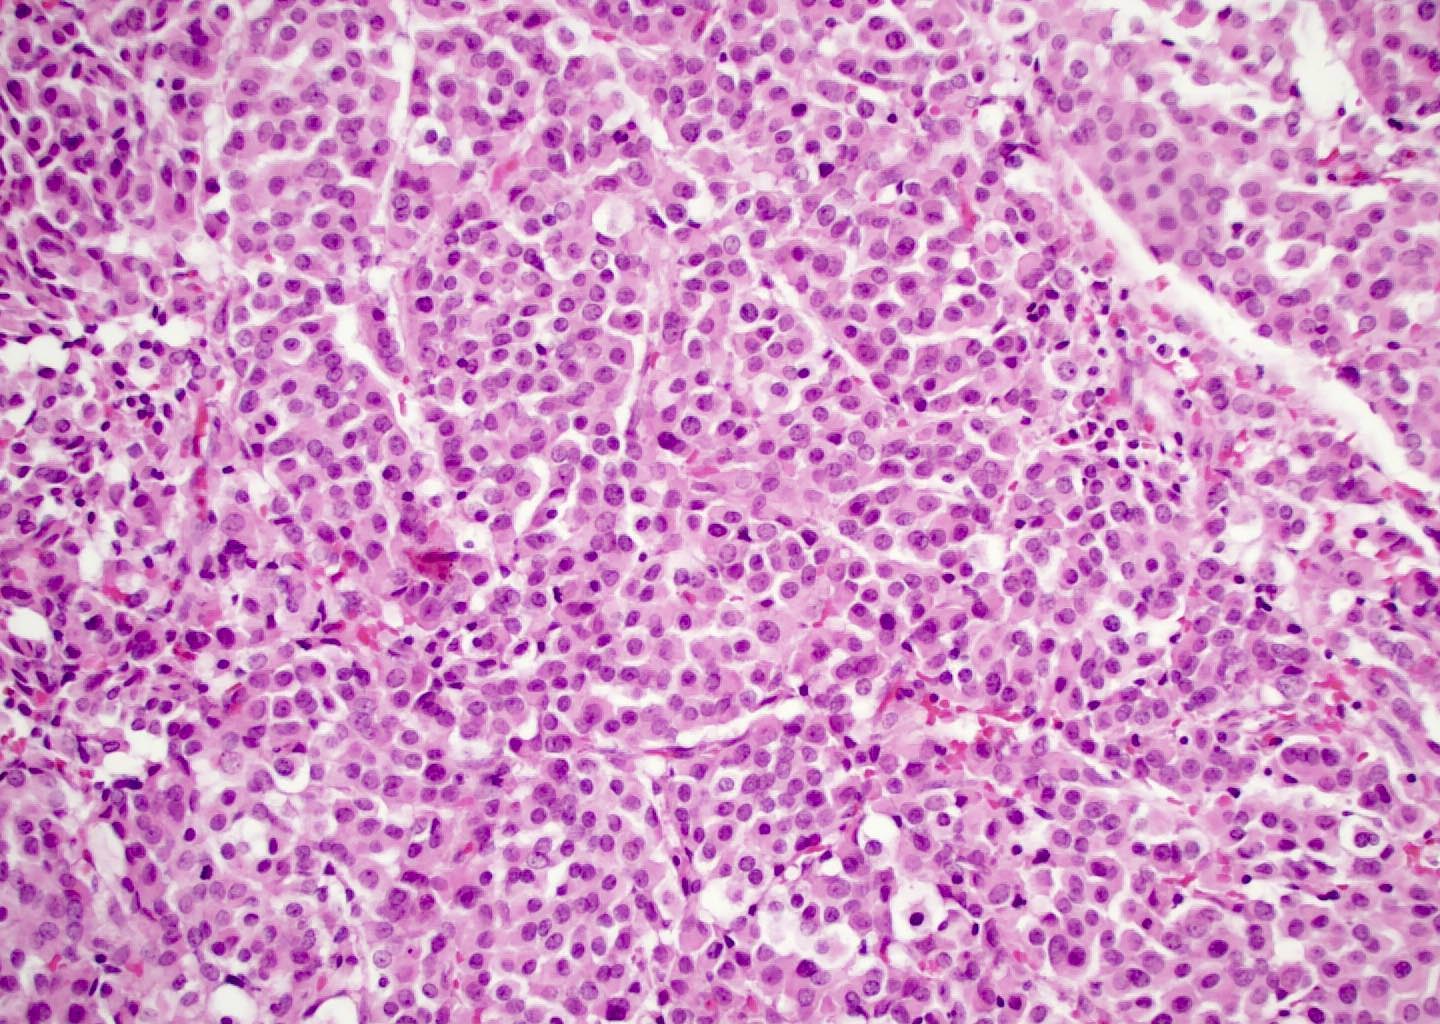
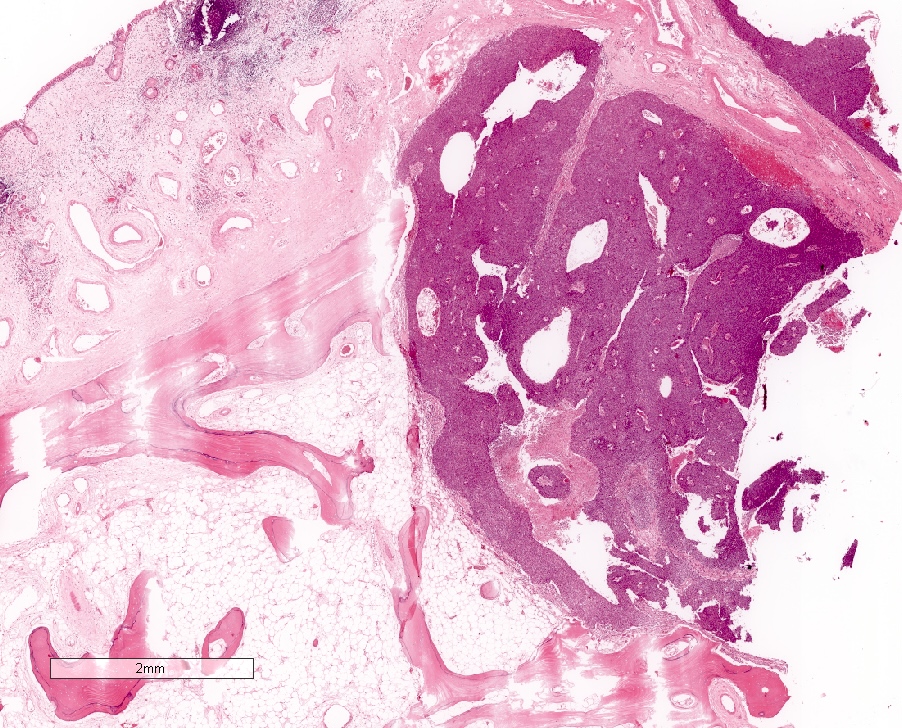
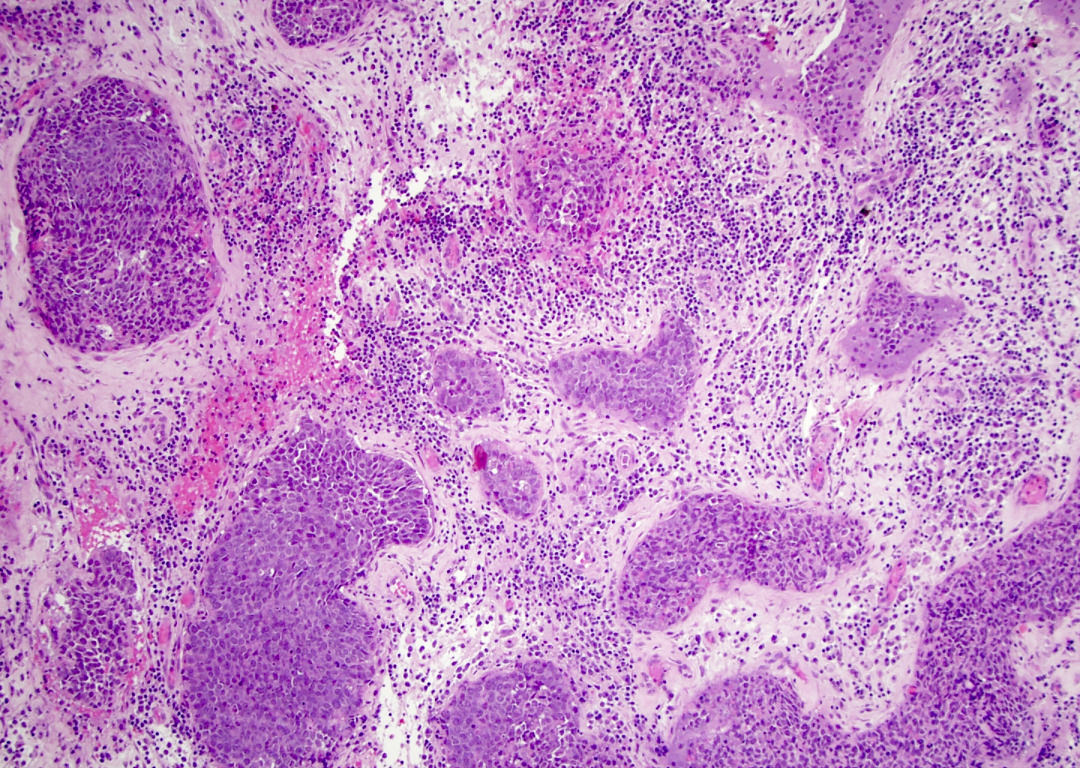
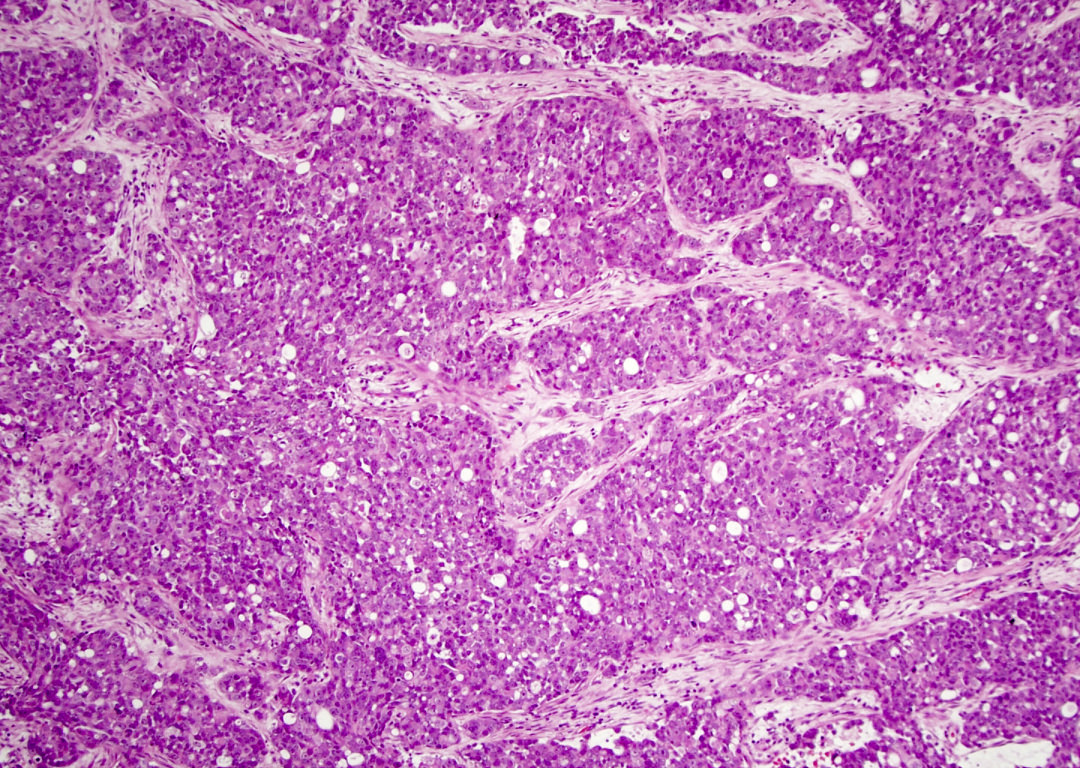
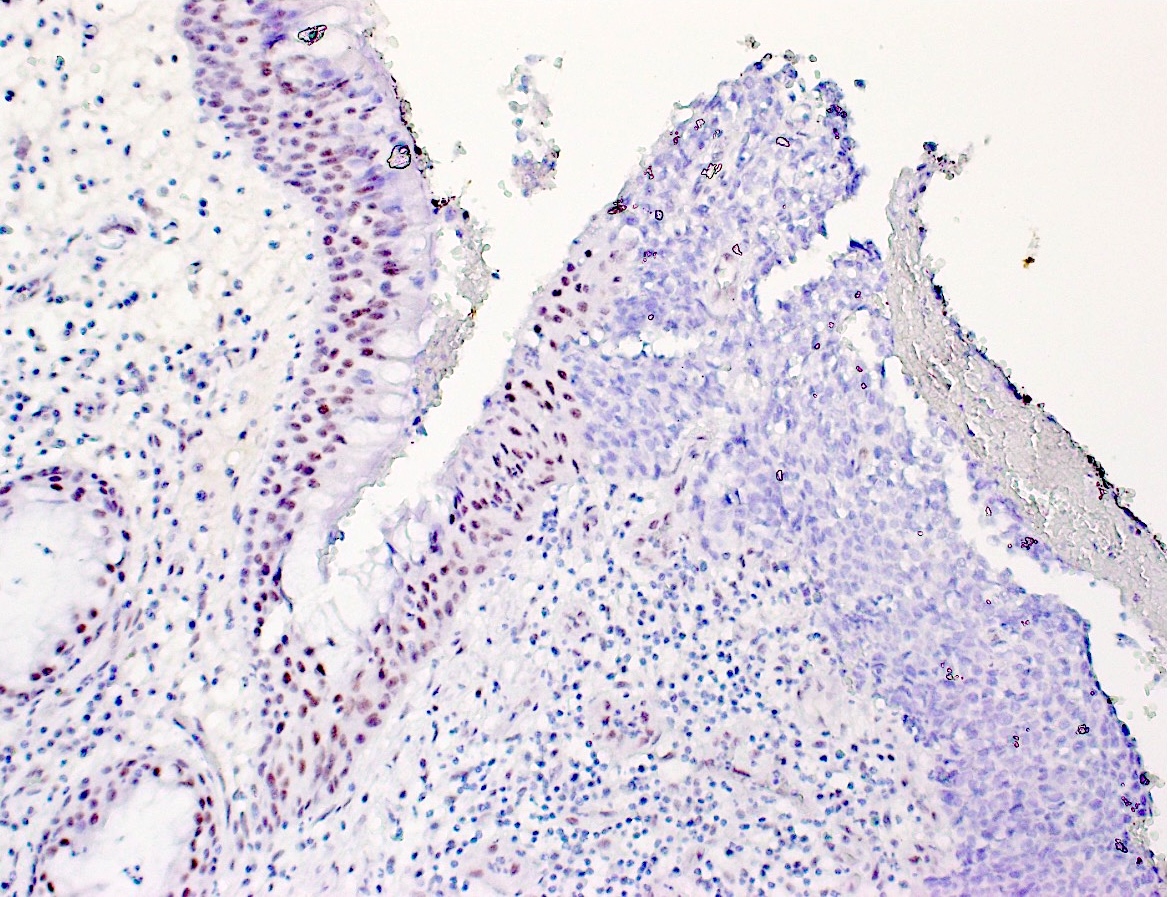
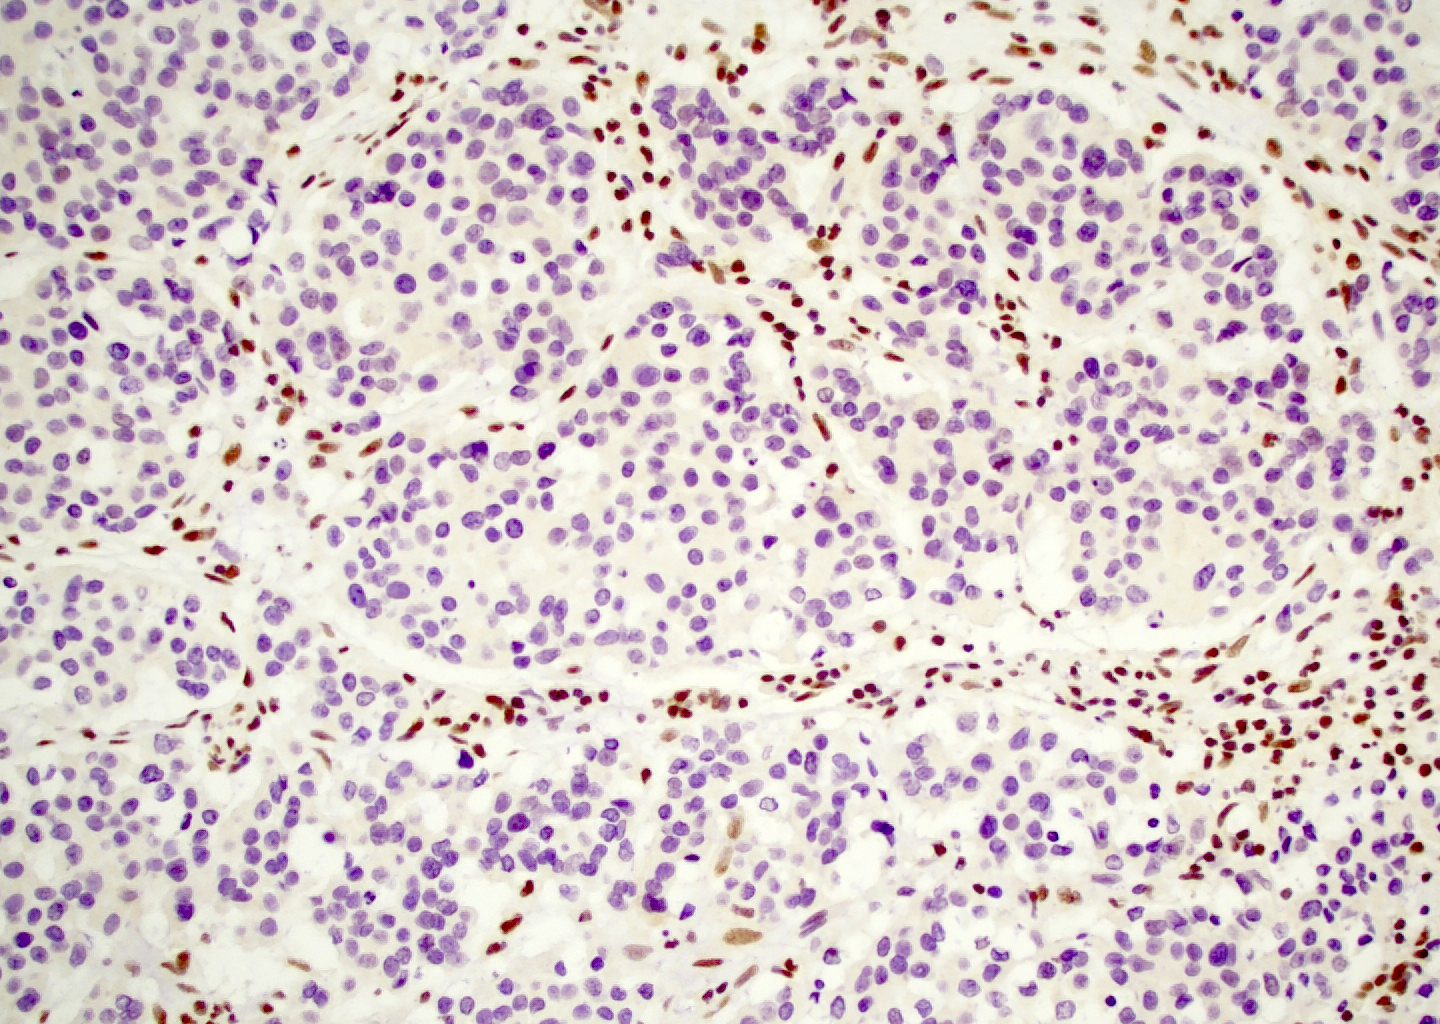
数字切片
供图:Jasmine Siaw · PathologyOutlines
细胞学描述
- 高级别恶性肿瘤。
- 涂片细胞丰富,可见黏附性多角形细胞团。
- 可见不同比例的散在横纹肌样 / 浆细胞样细胞,胞质丰富。
- 最常见的表现为细胞核均一、染色质细腻、核仁小。
- 无明显角化或其他鳞状分化证据(Diagn Cytopathol 2016;44:700)。
- 凋亡小体常见,背景有大量坏死碎屑(Cancer Cytopathol 2018;126:567)。
- SMARCA4 缺失型肿瘤预期可见多形性更明显的大型上皮样细胞。
细胞学图像
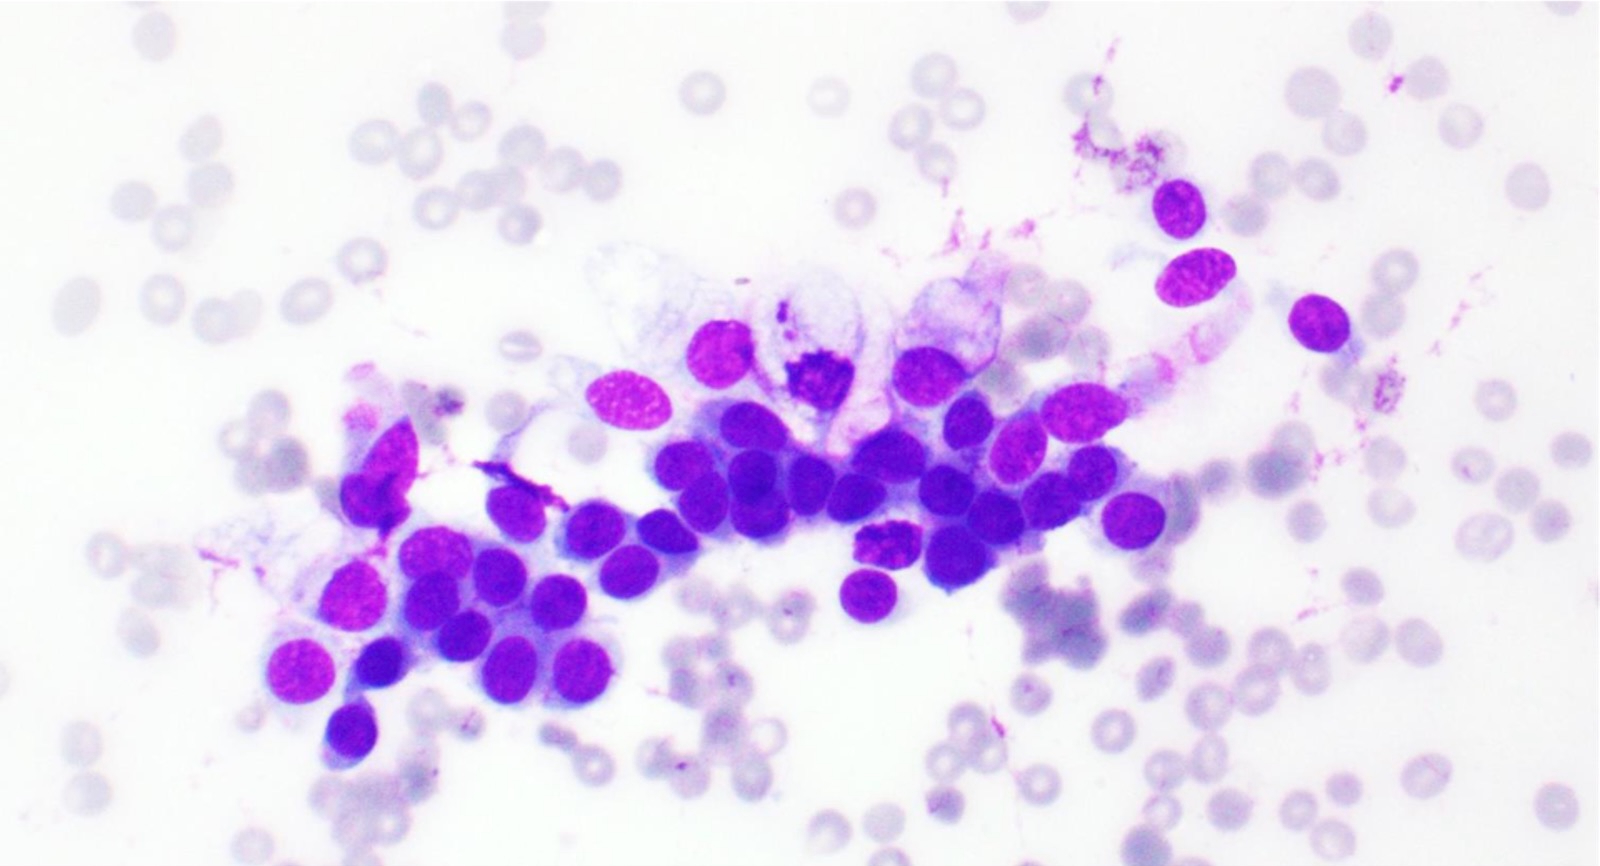
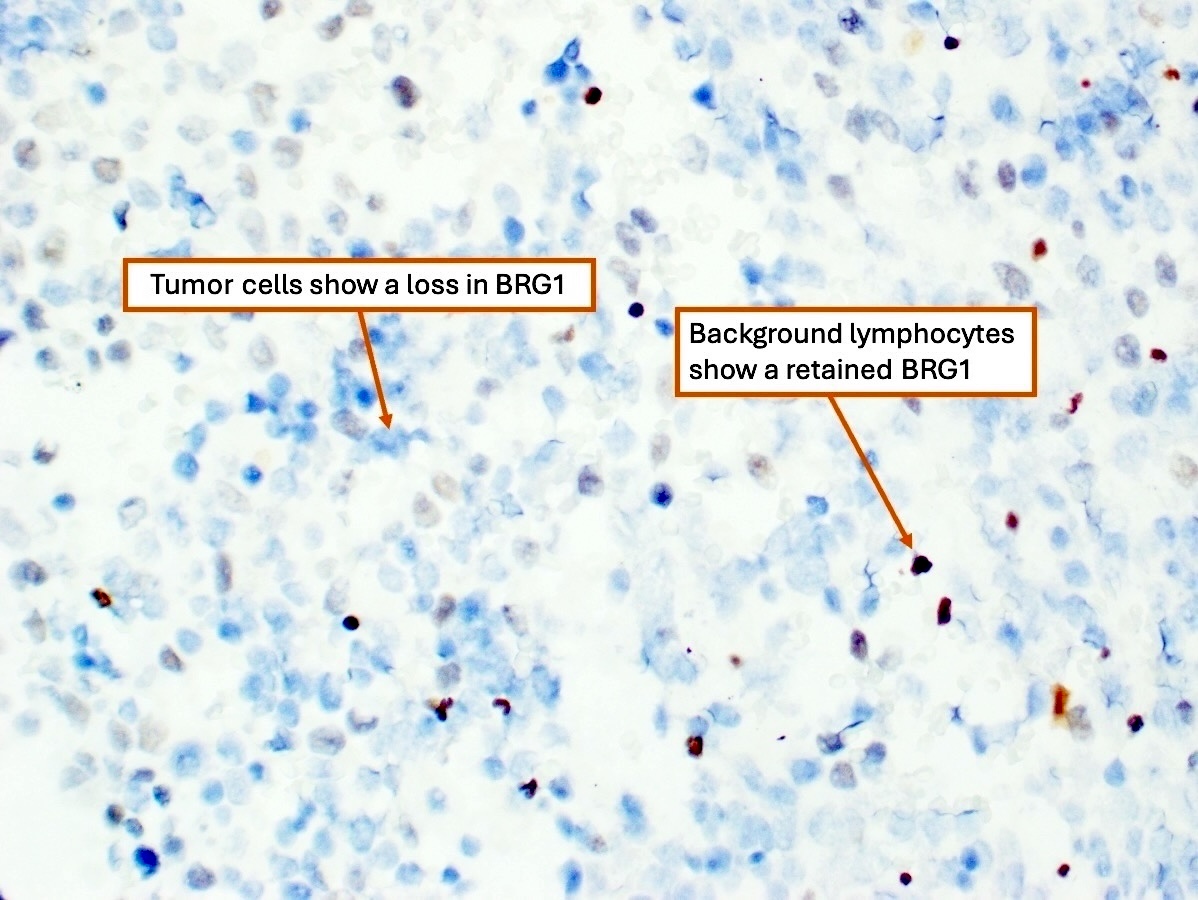
阳性染色
SMARCB1 缺失型鼻腔鼻窦癌
- 广谱细胞角蛋白(97%)。
- CK5(64%)、p63(55%)。
- p40 可呈强阳性。
SMARCB1 缺失型鼻腔鼻窦腺癌
- CK7(83%)。
- 不论有无相应形态,均可表达卵黄囊标记:磷脂酰肌醇蛋白聚糖 3(glypican 3,90%)、SALL4(50%)、HepPar1(50%)。
SMARCA4 缺失型鼻腔鼻窦癌
- 广谱细胞角蛋白。
- 神经内分泌标记局灶弱阳性:突触素(90%)、CD56(60%)。
阴性染色
SMARCB1 缺失型鼻腔鼻窦癌
- 定义为 SMARCB1(INI1)核表达缺失,内对照保留。
- 肌上皮染色阴性:S100、SOX10、钙调节蛋白、SMA。
- CK7(48%)。
- p16 通常阴性(Am J Surg Pathol 2014;38:1282)。
- IDH 阴性。
SMARCA4 缺失型鼻腔鼻窦癌
- 定义为 SMARCA4(BRG1)核表达缺失,内对照保留。
- p63、p16 通常阴性。
- 除鳞状区域外,p40 和 CK5/6 一般阴性。
- 嗜铬粒蛋白(40%)。
- INSM1 主要为阴性,或局灶弱阳性(Arch Pathol Lab Med 2022;146:1122;Am J Surg Pathol 2020;44:703)。
- NUT、CD99 均为阴性。
SMARCB1 缺失型鼻腔鼻窦腺癌
- p40(33%)(Head Neck Pathol 2020;14:465)。
- CDX2(27%)、CK20(25%)。
- 不论有无相应形态,卵黄囊标记:PLAP(11%)、AFP(10%)。
分子 / 细胞遗传学描述
SMARCB1 缺失型鼻腔鼻窦癌
- 定义为位于染色体 22q11.2 的抑癌基因 SMARCB1 发生失活性突变(Am J Surg Pathol 2014;38:1274;Am J Surg Pathol 2014;38:1282)。
- FISH 可检测涉及 SMARCB1 基因座的双等位基因(纯合)或单等位基因(杂合)缺失;但并非首选,因为免疫组化敏感性更高,且二代测序(NGS)可排除多种鉴别诊断(Head Neck Pathol 2022;16:168)。
SMARCA4 缺失型鼻腔鼻窦癌
- 无 IDH1/2 突变;文献报道的 IDH1/2 突变型抗体免疫阳性结果可能与突变检测不一致(Am J Surg Pathol 2020;44:703;Arch Pathol Lab Med 2022;146:1122)。
高危 HPV 及 EBV 原位杂交均为阴性(Am J Surg Pathol 2017;41:458)。
视频
病理报告示例
鼻腔肿块,半侧上颌骨切除术
- SMARCB1 缺失型鼻腔鼻窦癌(见评注及结构式报告)。
- 评注:半侧上颌骨切除标本切片显示高级别未分化肿瘤特征。肿瘤自左侧鼻腔呈外生性突出,并侵入上颌骨髓腔。
- 肿瘤由圆形大巢构成,巢内为片状重叠排列、形态单一的基底样细胞。染色质呈空泡状,核质比高,胞质极少。可见坏死及多处核分裂象。未见鳞状分化。
- 免疫组化显示 p40、CK5/6 阳性,SMARCA4(BRG1)表达保留。突触素局灶阳性。
- SMARCB1(INI1)免疫组化显示肿瘤细胞核表达弥漫缺失,内对照阳性。
- 肿瘤 p16、SOX10、CD99、结蛋白、MyoD1 和 NUT 阴性。
- 组织学特征及免疫表型符合 SMARCB1 缺失型鼻腔鼻窦癌。
鼻腔肿块,活检
- SMARCA4 缺失型鼻腔鼻窦癌(见评注)。
- 病变组织碎片显示高级别未分化肿瘤特征。
- 肿瘤由巢状排列的大型、多形性上皮样细胞构成。未见角化、色素形成、腺体形成等分化特征。亦未见其他成分(间叶及神经上皮成分)。
- 免疫组化显示 p40、CK5/6 和 SMARCB1 阳性(表达保留)。
- 突触素局灶阳性。肿瘤 p16、SOX10、CD99、结蛋白、MyoD1、NUT、CD45、CD56、CD20 和 TdT 阴性。
- SMARCA4(BRG1)免疫组化显示肿瘤细胞核表达弥漫缺失,内对照阳性。
- 肿瘤 EBER 及 HPV 原位杂交亦为阴性。
- 评注:虽然这些特征最符合 SMARCA4 缺失型鼻腔鼻窦癌,但不能排除畸胎癌肉瘤。
鉴别诊断
大多数与 SMARCA4 和 SMARCB1 鼻腔鼻窦癌相似的肿瘤,SMARCB1(INI1)和 SMARCA4 核免疫染色均保留。
高级别肠型及非肠型腺癌
- 腺样成分多少不等,并存在更特化的细胞,如杯状细胞及潘氏细胞。
- CK7 和 CEA 可不同程度阳性。
- SMARCB1(INI1)表达完整。
原发性及转移性卵黄囊瘤
- 极罕见,可伴有原发肿瘤病史。
- 类似鼻腔鼻窦癌的卵黄囊样形态。
- 磷脂酰肌醇蛋白聚糖 3(特异性较低,表达更多)、SALL4、PLAP。
- AFP 斑片状阳性。
- 腺样及肝样区域表达 HepPar1;腺样区域表达 CDX2。
- SMARCB1(INI1)表达保留。
转移性肝样腺癌
- 肝样区域的肝样分化标记阳性。
- 部位特异性染色,如肠道来源者 SATB2 阳性。
横纹肌肉瘤
- 骨骼肌标记:结蛋白、肌生成素。
- 分子改变:FOXO1 融合。
尤因肉瘤(尤其是造釉细胞瘤样变型)
- NKX2.2、CD99 阳性。
- 造釉细胞瘤样变型中 p63/p40、细胞角蛋白弥漫阳性。
- 突触素及嗜铬粒蛋白可阳性。
- 分子改变:EWSR1 融合。
淋巴瘤(如弥漫大 B 细胞淋巴瘤[DLBCL]、结外 NK/T 细胞淋巴瘤及急性淋巴母细胞白血病[ALL])
- 广谱淋巴细胞谱系标记:CD45。
- B 细胞标记:CD20。
- 前体淋巴细胞标记:TdT。
- 结外 NK/T 细胞淋巴瘤好发于东亚和拉丁美洲人群(Curr Hematol Malig Rep 2016;11:514)。
- NK/T 细胞淋巴瘤标记:T 细胞标记(如 CD56、CD2、CD3),EBER 原位杂交阳性。
黑色素瘤
- 可有色素;若为原发性,可有原位成分。
- HMB45、SOX10、MelanA、PRAME、S100 阳性。
鼻咽癌
- 可呈基底样及高级别形态。
- 鳞状标记阳性。
- EBER 原位杂交阳性。
鼻腔鼻窦未分化癌
- 高级别、未分化。
- EBER 原位杂交阴性。
- IDH2 突变可支持鼻腔鼻窦未分化癌,但 IDH 免疫组化应谨慎解读。
HPV 相关鼻腔鼻窦癌
- 多表型型具有基底及导管两种成分,呈双相结构。
- HPV 原位杂交阳性。
神经内分泌癌
- 高级别,伴核分裂象和坏死,可保留斑点状染色质。
- 神经内分泌标记(嗜铬粒蛋白、突触素)阳性。
- 细胞角蛋白呈点状染色。
嗅神经母细胞瘤
- 小圆细胞肿瘤,根据分化程度,可形成围绕真正肿瘤腔隙的 Flexner–Wintersteiner 菊形团,或围绕纤维状基质的 Homer Wright 菊形团。
- 位于筛窦筛板区域。
- 神经内分泌标记阳性。
- 支持细胞 S100 阳性。
NUT 癌
- 基底样外观,伴突然出现的角化。
- NUT 免疫组化阳性。
肌上皮癌(Head Neck Pathol 2022;16:168)
- 可呈横纹肌样 / 浆细胞样形态。
- 部分病例 SMARCB1(INI1)表达缺失。
- 肌上皮标记 S100、SOX10、SMA 和钙调节蛋白阳性。
SMARCA4 缺失型鼻腔鼻窦畸胎癌肉瘤
- 呈三相生长,具有上皮、间叶及原始神经上皮成分。
- 神经上皮成分:占优势,具有菊形团及神经毡样基质;嗜铬粒蛋白和突触素阳性。
- 上皮成分:成熟程度不一的鳞状上皮(从透明细胞胎儿型至成熟鳞状上皮)及腺体(黏液性、肠型或纤毛性);鳞状成分 CK5/6 阳性。
- 间叶成分:从未分化成纤维细胞性至横纹肌母细胞性;可有局灶软骨及骨组织。
- 有限活检材料中可能未见异源性、肉瘤样或畸胎样成分。
- SMARCA4(BRG1)缺失。
- 上皮细胞 β-连环蛋白核阳性。
| 肿瘤类型 | 细胞角蛋白 | 鳞状标记¹ | 神经内分泌标记² | 肌上皮标记 | CD99 | SWI/SNF 标记 | p16 | 其他 | 分子改变 |
|---|---|---|---|---|---|---|---|---|---|
| SMARCA4 / SMARCB1 鼻腔鼻窦癌 | + | + | 局灶弱阳性 | - | 局灶阳性 | 缺失 | 不定 | ||
| 横纹肌肉瘤 | + | - | - | - | 局灶阳性 | 保留 | - | 肌生成素及 MyoD1 阳性 | FOXO1 融合 |
| 尤因肉瘤 | + | + | - | - | + | 保留 | - | EWSR1:: FLI1 | |
| 淋巴瘤 | - | - | - | - | + | 保留 | - | 淋巴细胞标记³ | |
| 黑色素瘤 | - | - | - | - | + | 保留 | - | SOX10 +, HMB45 + | |
| 鼻咽癌 | HMWCK + | + | - | - | 不定 | 保留 | + | EBV 原位杂交 | |
| 鼻腔鼻窦未分化癌 | + | - | - | - | 保留 | 不定 | IDH2 + | ||
| HPV 相关鼻腔鼻窦癌 | HMWCK + | + | 阴性 / 斑片状阳性 | + | 保留 | + | 其他谱系标记阴性,包括 NUT | HPV 原位杂交 | |
| 神经内分泌癌 | 点状阳性 | - | + | - | 保留 | - | |||
| 嗅神经母细胞瘤 | 局灶阳性 | - | + | 支持细胞 S100 阳性 | - | 保留 | EMA - | ||
| NUT 癌 | + | + | 不定且较弱 | - | - | 保留 | + | NUT + | |
| 肌上皮癌 | AE1 / AE3 + | p63 表达不定 | + | INI1 可缺失 | EMA +, GFAP + | PLAG1 融合、EWSR1 重排 |
¹ 鳞状标记:CK5/6、p40。
² 神经内分泌标记:嗜铬粒蛋白、突触素、INSM1。
³ 淋巴细胞标记:CD45(广谱白细胞标记)、CD3(广谱 T 细胞标记)、CD20(B 细胞标记)。
其他参考文献
WHO 肿瘤分类编委会:《头颈部肿瘤》,第 5 版,2024 年。
练习题 1
收到一份鼻腔肿瘤活检。影像显示破坏性骨质侵犯,并累及邻近鼻腔鼻窦区域。下列关于 SWI/SNF 复合体缺失型鼻腔鼻窦癌诊断的说法,哪项正确?
- 若活检未见畸胎样成分,肿瘤细胞核 BRG1 缺失且对照阳性,即可诊断 SMARCA4 缺失型鼻腔鼻窦癌。
- 肿瘤细胞及呼吸上皮中 BRG1 均缺失,支持 SMARCA4 缺失型鼻腔鼻窦癌的诊断。
- 肿瘤细胞及内对照细胞 INI1 表达保留,支持 SMARCB1 缺失型鼻腔鼻窦癌的诊断。
- 仅有卵黄囊分化及 INI1 缺失,即可诊断 SMARCB1 缺失型鼻腔鼻窦腺癌。
- 上皮下菊形团及弥漫神经内分泌标记表达,支持 SMARCB1 缺失型鼻腔鼻窦癌的诊断。
练习题 1 答案
D.仅有卵黄囊分化及 INI1 缺失,即可诊断 SMARCB1 缺失型鼻腔鼻窦腺癌。存在卵黄囊分化时,并非必须有腺样分化。
B 错误:呼吸上皮(内对照)BRG1 缺失提示免疫组化染色失败,因此必须重复染色。
C 错误:SMARCB1 缺失型鼻腔鼻窦癌的定义是 SMARCB1(INI1)核表达缺失。本例肿瘤细胞 INI1 保留,且内对照适当,故排除 SMARCB1 缺失。
E 错误:SMARCB1 缺失型鼻腔鼻窦癌在占据上皮下腺体时可形成菊形团,但神经内分泌标记应仅局灶阳性。弥漫神经内分泌标记阳性不常见,应怀疑嗅神经母细胞瘤。
A 错误:这是活检;有限活检标本可能未取到异源性成分,因此 SMARCA4 缺失型鼻腔鼻窦癌与 SMARCA4 缺失型畸胎癌肉瘤可能无法区分。
练习题 2
下列关于 SMARCB1 缺失型鼻腔鼻窦癌的描述,哪项正确?
- 以 p16 免疫组化及高危 HPV RNA 原位杂交弥漫阳性为特征。
- 以 BRG1 缺失定义。
- 呈 Paget 样分布的真正表面上皮异型增生。
- 可见周边栅栏状排列的基底样细胞巢,且 p40 强阳性。
练习题 2 答案
D.可见周边栅栏状排列的基底样细胞巢,且 p40 强阳性。因此,SMARCB1 缺失型鼻腔鼻窦癌可模拟基底样鳞状细胞癌。
A 错误:虽然 SMARCB1 缺失型鼻腔鼻窦癌的 p16 免疫组化可弥漫阳性,但高危 HPV RNA 原位杂交不应阳性。p16 弥漫阳性并伴高危 HPV RNA 原位杂交阳性,支持 HPV 相关鼻腔鼻窦癌;单独 p16 不能作为 HPV 的替代指标,其他肿瘤也可过表达。
C 错误:虽然肿瘤可向上呈 Paget 样播散,但这并不代表真正的异型增生。
B 错误:SMARCB1 缺失型鼻腔鼻窦癌的定义是 SMARCB1(INI1)核表达缺失。
Definition / general
- SWI / SNF complex deficient sinonasal carcinomas encompass poorly differentiated to undifferentiated epithelial tumors in the sinonasal tract with loss of SMARCB1 (INI1) or SMARCA4 (BRG1) protein expression (Adv Anat Pathol 2023;30:95, AJNR Am J Neuroradiol 2023;44:1116)
Essential features
- Arising from the sinonasal tract
- Defining feature is loss of SMARCB1 (INI1) or SMARCA4 (BRG1) protein expression
- 3 recognized subtypes
- SMARCB1 deficient sinonasal carcinoma
- SMARCB1 deficient sinonasal adenocarcinoma (at least focal glandular or yolk sac morphology is essential)
- SMARCA4 deficient sinonasal carcinoma
- Aggressive clinical course
Terminology
- Sinonasal undifferentiated carcinoma (previous terminology; currently not recommended)
ICD coding
- ICD-O: 8044/3 - SWI / SNF complex deficient sinonasal carcinoma
- ICD-10
- ICD-11
- 2C20.Z & XH1YY4 - malignant neoplasms of nasal cavity, unspecified & carcinoma, undifferentiated, NOS
- 2C22.2 & XH1YY4 - malignant neoplasms of accessory sinuses, unspecified & carcinoma, undifferentiated, NOS
Epidemiology
- Male predominance across all subtypes
- Broad age range (young adults to elderly) (Am J Surg Pathol 2017;41:458, Head Neck Pathol 2022;16:168)
Sites
- SMARCA4 deficient sinonasal carcinoma and SMARCB1 deficient sinonasal adenocarcinoma
- Nasal cavity with multiple sinonasal sites (Head Neck Pathol 2022;16:168)
- SMARCB1 deficient sinonasal carcinoma
- Paranasal sinuses (mainly ethmoid), variably involves nasal cavity (Am J Surg Pathol 2017;41:458)
Pathophysiology
- Switch / sucrose nonfermentable (SWI / SNF) chromatin remodeling complex functions as a tumor suppressor and is composed of proteins encoded by > 20 genes
- Several mutations are seen with gene specific clustering; 2 subunit alterations of most relevance to the sinonasal tract are SMARCB1 and SMARCA4
- SMARCB1 deficiency from biallelic deletion or inactivation at chromosome 22q11.2
- SMARCA4 deficiency from biallelic inactivation at chromosome 19p13.2 (Head Neck Pathol 2022;16:168)
Etiology
- Not known
Clinical features
- Clinically mimics benign conditions with mild congestive symptoms
- Becomes clinically apparent due to mass effect with compression of cranial nerves and branches (Cancers 2022;14:3285)
- Locally aggressive, often presenting at T4 with invasion into the orbit and intracranium
Diagnosis
- While cytology can theoretically be adequate for diagnosis, a cell block is required for pertinent immunohistochemistry
- Sampling issues render a cytology or histology based diagnosis difficult (Head Neck Pathol 2022;16:168)
- Glandular or yolk sac elements are required for diagnosis of SMARCB1 deficient sinonasal adenocarcinoma
- Excision may allow more complete assessment of morphology when limited biopsy material is nondiagnostic
- WHO histological criteria for diagnosis
- Essential: sinonasal tract location; undifferentiated carcinoma with SMARCB1 (INI1) or SMARCA4 (BRG1) loss but no features of other entities; unequivocal gland formation or yolk sac tumor-like features are required for the adenocarcinoma subtype
- Desirable: presence of rhabdoid cells; yolk sac-like features for the adenocarcinoma variant
Radiology description
- T4 stage at presentation with involvement of multiple sinuses, adjacent orbital and intracranial compartments
- Avid enhancement, intermediate T2 signal intensity, moderate diffusion restriction and fluorodeoxyglucose (FDG) avidity
- Blurring of anatomic boundaries with osseous change
- CT imaging showing calcification likely reflects retained bone fragments or an aggressive periosteal reaction causing a hair on end appearance
- Reference: AJNR Am J Neuroradiol 2016;37:1925
Radiology images
Prognostic factors
- SMARCB1 deficient sinonasal carcinoma
- Mortality rate of 56% at 16 months (Am J Surg Pathol 2017;41:458)
- Unresectable disease and metastasis are the most common causes of death
- T4 disease and male gender are associated with worse prognosis
- SMARCB1 deficient sinonasal adenocarcinoma
- Not currently defined due to limited follow up data
- SMARCA4 deficient sinonasal carcinoma
- Highly aggressive with comparable behavior to extrasinonasal counterparts
- ~67% of patients are deceased within a year of diagnosis (Arch Pathol Lab Med 2022;146:1122)
Case reports
- 53 year old man with endobronchial metastases (Acta Cytol 2019;63:431)
- 54 year old woman with persistent left sided symptoms including epistaxis, hemicrania and ocular symptoms (Pathol Int 2022;72:53)
- 58 year old man presented with right sided nasal congestion, decreased sense of smell and protrusion of the right eyeball (Diagn Pathol 2025;20:102)
- 64 year old man with worsening right sided headache and sixth nerve palsy (Cureus 2025;17:e77217)
- 72 year old man with left facial pain and nasal obstruction, develops lung metastasis (J Surg Case Rep 2021;2021:rjab161)
Treatment
- Multimodal therapy: resection, chemotherapy and radiotherapy (Cancers 2022;14:3285)
- Induction chemotherapy reduces the risk of distant metastasis and good response to induction chemotherapy is associated with a good subsequent response to radiotherapy
- Patients who proceeded to definitive chemoradiotherapy had better survival outcomes than with a primary resection
- In cases with a poor response to induction chemotherapy, resection was then pursued (J Clin Oncol 2019;37:504)
- Targeted therapies addressing downstream alterations related to SWI / SNF complex deficiency are under investigation
- EZH2 activity is increased following loss of SMARCB1 protein expression, making EZH2 a therapeutic target for small molecule inhibitors (Cancers 2022;14:3285)
Gross description
- Often presents as T4 disease with highly infiltrative growth and bony invasion of local structures (i.e., maxilla) (AJNR Am J Neuroradiol 2016;37:1925)
- Can have an exophytic papilliform surface (Am J Surg Pathol 2017;41:458)
Gross images
Frozen section description
- Undifferentiated high grade malignancy on frozen
- Can be used to assess margin status in the setting of a known diagnosis
Microscopic (histologic) description
SMARCB1 deficient sinonasal carcinoma (Head Neck Pathol 2022;16:168)
- Monomorphic with predominant basaloid morphology (60% of cases)
- Peripheral palisading (indistinguishable from basaloid squamous cell carcinoma [SCC]) (Am J Surg Pathol 2017;41:458)
- Eosinophilic, plasmacytoid / rhabdoid morphology (30% of cases) (Am J Surg Pathol 2017;41:458)
- Absent squamous differentiation (lack of keratinization and conventional morphology)
- Rare clear and spindled cells
- Pagetoid spread along the mucosa (carcinoma in situ mimic) may occur but there should be no true surface dysplasia
- May exhibit papilliform growth with colonization of mucous glands imparting an inverted appearance
SMARCB1 deficient sinonasal adenocarcinoma (Head Neck Pathol 2020;14:465)
- Unequivocal gland formation defined by tubules, cribriform pattern and intraluminal or intracellular lumen documented in 5 - 100% of tumor
- Occasional yolk sac (microcystic / reticular in a myxoid background) appearance
- Predominant oncocytoid / plasmacytoid morphology with myxoid stroma
- High grade cytology with nuclear pleomorphism, necrosis and mitoses
- Rarely spindled, squamoid or clear cell in appearance
SMARCA4 deficient sinonasal carcinoma (Head Neck Pathol 2022;16:168)
- Sheets of large, epithelioid, anaplastic cells
- Variable nesting and trabecular pattern
- Lack of glandular and squamous differentiation
- Brisk mitotic activity and extensive necrosis
- Rarely can have abortive neuroendocrine-like rosettes
- Only a minority of cells should be basaloid and rhabdoid but these features can predominate
Microscopic (histologic) images
Virtual slides
Contributed by Jasmine Siaw · PathologyOutlines
Cytology description
- High grade malignant neoplasm
- Hypercellular smears with clusters of cohesive polygonal cells
- Variable proportion of individual rhabdoid / plasmacytoid cells with abundant cytoplasm
- Most commonly presents with uniform nuclei with fine chromatin and small nucleoli
- No overt keratinization or other evidence of squamous differentiation (Diagn Cytopathol 2016;44:700)
- Apoptotic bodies common with abundant background necrotic debris (Cancer Cytopathol 2018;126:567)
- For SMARCA4 tumors, large epithelioid cells with a more pleomorphic appearance are expected
Cytology images
Positive stains
SMARCB1 deficient sinonasal carcinoma
- Pancytokeratins (97%)
- CK5 (64%), p63 (55%)
- May show strong p40 positivity
SMARCB1 deficient sinonasal adenocarcinoma
- CK7 (83%)
- Yolk sac markers regardless of morphological expression: glypican 3 (90%), SALL4 (50%), HepPar1 (50%)
SMARCA4 deficient sinonasal carcinoma
- Pancytokeratin
- Focal and weak neuroendocrine markers: synaptophysin (90%), CD56 (60%)
Negative stains
SMARCB1 deficient sinonasal carcinoma
- Defined by loss of nuclear SMARCB1 (INI1) expression with retained internal control
- Negative for myoepithelial stains (S100, SOX10, calponin, SMA)
- CK7 (48%)
- Usually negative for p16 (Am J Surg Pathol 2014;38:1282)
- Negative for IDH
SMARCA4 deficient sinonasal carcinoma
- Defined by loss of nuclear SMARCA4 (BRG1) expression with retained internal control
- Usually negative: p63, p16
- p40 and CK5/6 generally negative unless in squamous area
- Chromogranin (40%)
- INSM1 is mainly negative or focally positive with weak intensity (Arch Pathol Lab Med 2022;146:1122, Am J Surg Pathol 2020;44:703)
- Consistently negative for NUT, CD99
SMARCB1 deficient sinonasal adenocarcinoma
Molecular / cytogenetics description
- SMARCB1 deficient sinonasal carcinoma
- Defined by inactivating mutations of SMARCB1 gene, a tumor suppressor gene located on chromosome 22q11.2 (Am J Surg Pathol 2014;38:1274, Am J Surg Pathol 2014;38:1282)
- FISH can detect biallelic (homozygous) or monoallelic (heterozygous) deletions affecting the SMARCB1 gene locus (not preferred due to IHC with greater sensitivity and multiple differentials that can be ruled out with next generation sequencing [NGS]) (Head Neck Pathol 2022;16:168)
- SMARCA4 deficient sinonasal carcinoma
- IDH1 / 2 mutations are absent; reported IDH1 / 2 mutant antibody immunopositivity may not correlate with mutation testing (Am J Surg Pathol 2020;44:703, Arch Pathol Lab Med 2022;146:1122)
- In situ hybridization for high risk HPV and EBV is consistently negative (Am J Surg Pathol 2017;41:458)
Videos
- Brief overview of SMARCB1 deficient sinonasal carcinoma
- SMARCB1 deficient sinonasal carcinoma discussion
- SMARCB1 deficient sinonasal carcinoma case report
Sample pathology report
- Nasal mass, hemimaxillectomy:
- SMARCB1 deficient sinonasal carcinoma (see comment and synoptic report)
- Comment: The sections from the hemimaxillectomy show features of a high grade undifferentiated neoplasm. It protrudes in an exophytic manner from the left nasal cavity and invades into the medullary bone of the maxilla.
- The tumor is composed of rounded large nests with sheets of overlapping, monomorphic basaloid cells. They contain vesicular chromatin, high nuclear to cytoplasmic ratio and minimal cytoplasm. Necrosis and multiple mitoses are seen. Squamous differentiation is not seen.
- Immunohistochemistry shows positive staining for p40, CK5/6 with retained SMARCA4 (BRG1) expression. There is focal staining for synaptophysin.
- Immunohistochemistry for SMARCB1 (INI1) shows diffuse loss of nuclear expression in the tumor cells (with positive internal control).
- The tumor is negative for p16, SOX10, CD99, desmin, MyoD1 and NUT.
- The histological features and immunoprofile are in keeping with a SMARCB1 deficient sinonasal carcinoma.
- Nasal mass, biopsy:
- SMARCA4 deficient sinonasal carcinoma (see comment)
- The lesional fragments show features of a high grade, undifferentiated neoplasm.
- It is composed of large, pleomorphic, epithelioid cells in a nested architecture. Features of differentiation (i.e., keratinization, pigmentation, glandular formation) are not seen. Additional components (mesenchymal and neuroepithelial) are also not seen.
- Immunohistochemistry shows positive staining for p40, CK5/6 and SMARCB1 (retained).
- There is focal staining for synaptophysin. The tumor is negative for p16, SOX10, CD99, desmin, MyoD1, NUT, CD45, CD56, CD20 and TdT.
- Immunohistochemistry for SMARCA4 (BRG1) shows diffuse loss of nuclear expression in the tumor cells (with positive internal control).
- The tumor is also negative for EBER in situ hybridization and HPV in situ hybridization.
- Comment: While these features are most in keeping with a SMARCA4 deficient sinonasal carcinoma, a teratocarcinosarcoma cannot be excluded.
Differential diagnosis
- Most mimics of SMARCA4 and SMARCB1 sinonasal carcinomas show retained nuclear immunostaining with SMARCB1 (INI1) and SMARCA4
- High grade intestinal and nonintestinal adenocarcinoma:
- Variable glandular component with more specialized cells present (i.e., goblet and Paneth)
- CK7 and CEA are variably positive
- SMARCB1 (INI1) is intact
- Primary and metastatic yolk sac tumor:
- Extremely rare and will be accompanied by a history of a primary
- Resembles the yolk sac appearance of sinonasal carcinomas
- Glypican 3 (less specific, more expression), SALL4, PLAP
- AFP patchy positive
- HepPar1 in glandular and hepatoid areas; CDX2 in glandular areas
- SMARCB1 (INI1) retained
- Metastatic hepatoid adenocarcinoma:
- Hepatoid areas positive for hepatoid stains
- Site specific stain (i.e., SATB2 positivity in gut)
- Rhabdomyosarcoma:
- Ewing sarcoma (especially adamantinoma-like):
- NKX2.2, CD99 positive
- Diffuse positive in adamantinoma-like variant: p63 / p40, cytokeratin
- Synaptophysin and chromogranin can be positive
- Molecular: EWSR1 fusion
- Lymphoma (i.e., diffuse large B cell lymphoma [DLBCL], extranodal NK / T cell lymphoma and ALL):
- Broad spectrum lymphoid lineage marker: CD45
- B cell markers: CD20
- Precursor lymphoid marker: TdT
- Extranodal NK / T cell lymphomas have an East Asian and Latin American predilection (Curr Hematol Malig Rep 2016;11:514)
- NK / T cell lymphoma markers: T cell markers (i.e., CD56, CD2, CD3), EBER in situ hybridization positive
- Melanoma:
- Nasopharyngeal carcinoma:
- Can appear basaloid and high grade
- Positive for squamous markers
- Positive for EBER in situ hybridization
- Sinonasal undifferentiated carcinoma:
- HPV related sinonasal carcinoma:
- Multiphenotypic type has a biphasic basal and ductal component
- Positive for HPV in situ hybridization
- Neuroendocrine carcinoma:
- High grade with mitosis and necrosis, may retain speckled chromatin
- Positive for neuroendocrine markers (chromogranin and synaptophysin)
- Dot-like cytokeratin pattern
- Olfactory neuroblastoma:
- Small round cell tumor with rosettes around true tumor lumens (Flexner-Wintersteiner rosettes) or fibrillary matrix (Homer Wright rosettes) depending on level of differentiation
- Based on the ethmoid sinus cribriform plate
- Positive for neuroendocrine markers
- S100 positive in sustentacular cells
- NUT carcinoma:
- Basaloid appearance with abrupt keratinization
- Positive for NUT IHC
- Myoepithelial carcinoma (Head Neck Pathol 2022;16:168):
- Can show rhabdoid / plasmacytoid morphology
- Subset shows loss of SMARCB1 (INI1)
- Positive for myoepithelial markers S100, SOX10, SMA and calponin
- High grade intestinal and nonintestinal adenocarcinoma:
- SMARCA4 deficient sinonasal teratocarcinosarcoma:
- Triphasic growth with epithelial, mesenchymal and primitive neuroepithelial elements
- Neuroepithelial component: predominant with rosettes and neuropil-like matrix; positive for chromogranin and synaptophysin
- Epithelial component: squamous epithelium of varying maturity (clear cell fetal type to mature squamous) and glands (mucinous, intestinal type or ciliated); squamous component is positive for CK5/6
- Mesenchymal component: undifferentiated fibroblastic to rhabdomyoblastic; can have foci of cartilage and bone
- Heterologous, sarcomatoid or teratoid elements may be absent in limited biopsy material
- SMARCA4 (BRG1) loss
- Beta catenin nuclear positivity in epithelial cells
| Entity | Cytokeratins | Squamous markers 1 | Neuroendocrine markers 2 | Myoepithelial markers | CD99 | SWI / SNF markers | p16 | Other | Molecular |
|---|---|---|---|---|---|---|---|---|---|
| SMARCA4 / SMARCB1 sinonasal carcinoma | + | + | Focal weak + | - | Focal + | Loss | Variable | ||
| Rhabdomyosarcoma | + | - | - | - | Focal + | Retained | - | Myogenin and MyoD1 + | FOXO1 fusion |
| Ewing sarcoma | + | + | - | - | + | Retained | - | EWSR1:: FLI1 | |
| Lymphoma | - | - | - | - | + | Retained | - | Lymphoid markers 3 | |
| Melanoma | - | - | - | - | + | Retained | - | SOX10 +, HMB45 + | |
| Nasopharyngeal carcinoma | HMWCK + | + | - | - | Variable | Retained | + | EBV in situ hybridization | |
| Sinonasal undifferentiated carcinoma | + | - | - | - | Retained | Variable | IDH2 + | ||
| HPV related sinonasal carcinoma | HMWCK + | + | - / patchy + | + | Retained | + | Negative for other lineages, including NUT | HPV in situ hybridization | |
| Neuroendocrine carcinoma | Dot-like + | - | + | - | Retained | - | |||
| Olfactory neuroblastoma | + focally | - | + | S100 + in sustentacular cells | - | Retained | EMA - | ||
| NUT carcinoma | + | + | Variable and weak | - | - | Retained | + | NUT + | |
| Myoepithelial carcinoma | AE1 / AE3 + | Variable p63 | + | INI1 can be lost | EMA +, GFAP + | PLAG1 fusion, EWSR1 rearrangement |
2Neuroendocrine markers: chromogranin, synaptophysin, INSM1
3Lymphoid markers: CD45 (broad spectrum leukocyte marker), CD3 (broad spectrum T cell), CD20 (B cell marker)
Additional references
Practice question #1
You receive a biopsy of a nasal tumor. Imaging shows destructive bony growth and involvement of adjacent sinonasal compartments. Which of the following statements regarding the diagnosis of SWI / SNF complex deficient sinonasal carcinoma is correct?
- BRG1 loss in tumor nuclei with positive controls is diagnostic of SMARCA4 deficient sinonasal carcinoma if no teratoid elements are present in the biopsy
- Loss of BRG1 in tumor cells and respiratory epithelium supports the diagnosis of SMARCA4 deficient sinonasal carcinoma
- Retained INI1 expression in tumor cells and internal control cells supports the diagnosis of SMARCB1 deficient sinonasal carcinoma
- SMARCB1 deficient sinonasal adenocarcinoma can be diagnosed with only yolk sac differentiation and INI1 loss
- Subepithelial rosettes and diffuse neuroendocrine expression support the diagnosis of SMARCB1 deficient sinonasal carcinoma
Practice answer #1
Reference: SWI / SNF complex deficient sinonasal carcinoma
Practice question #2
- Characterized by diffuse positivity for p16 immunohistochemistry and high risk HPV RNA in situ hybridization
- Defined by loss in BRG1
- Demonstrates a true surface dysplasia in the form of a pagetoid distribution
- May show basaloid cell nests with peripheral palisading and strong p40 positivity
Practice answer #2
Reference: SWI / SNF complex deficient sinonasal carcinoma