- zolbetuximab 资格阈值:>75% 肿瘤细胞呈 2+ 或 3+ 膜染色;六位消化病理医师评估非连续 47 例与连续 48 例数字化切片。
- 总体 H-score 一致性良好(两队列 ICC 0.85 / 0.91);资格判定实质一致(Fleiss kappa 0.63 / 0.72)。
- 较弱染色强度(尤其 1+)与染色异质性是主要变异来源;提示标准评分与困难病例共识判读。
收录范围:仅 PubMed 英文摘要及中文翻译(abstract-only);ScienceDirect 全文受 Cloudflare 限制,未采集全文或全文图表。X 配图来自 @Human_Pathology 推文卡片。
摘要
表达 claudin 18.2(CLDN18)的胃食管腺癌可成为 zolbetuximab 等靶向治疗的候选。达到一定阈值的 CLDN18 免疫组化染色用于确定治疗资格。本研究旨在评估病理医师在判读 CLDN18 免疫染色时的观察者间变异。
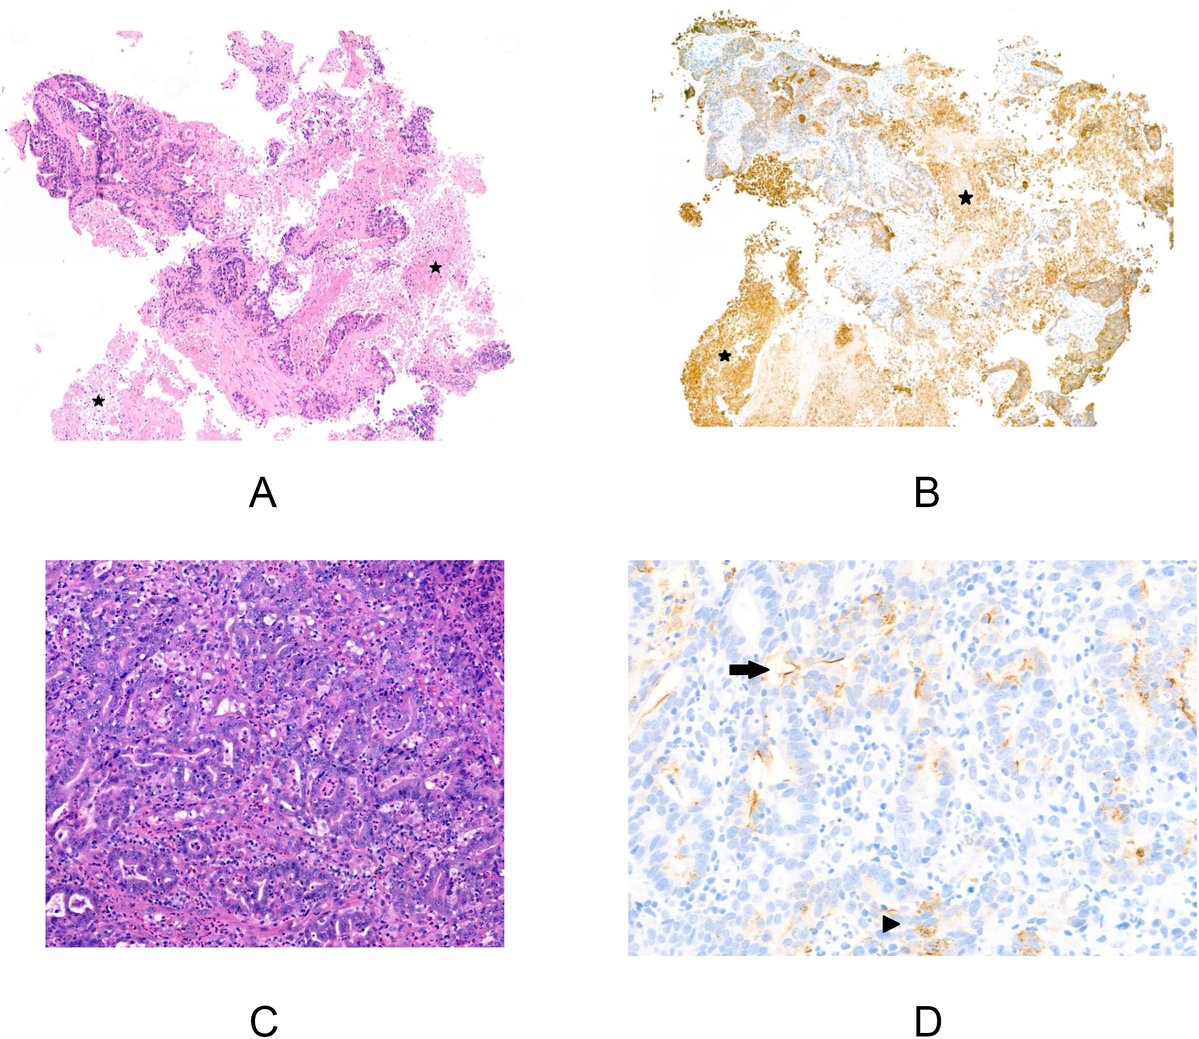
六位消化病理医师对非连续队列 47 例与连续队列 48 例胃食管腺癌的数字化扫描切片进行 CLDN18 染色评估。每位评分者估计呈 0、1+、2+ 或 3+ 膜染色强度的肿瘤细胞百分比(据此计算总体 H-score),并判定是否按 zolbetuximab 资格阈值(>75% 肿瘤细胞呈 2+ 或 3+ 染色)判为阳性。同时记录可能影响评分的因素,如染色异质性以及技术或取材因素。观察者间一致性分别以 kappa 统计量(分类评分)与组内相关系数(ICC,连续指标)评估。
总体 H-score 的观察者间一致性良好,两队列 ICC 分别为 0.85 与 0.91。关于是否符合 zolbetuximab 治疗资格,观察者间一致性为实质一致(两队列 Fleiss kappa 分别为 0.63 与 0.72)。非连续队列中,全部评分者完全一致的病例为 32 例(68%)(符合资格 8 例,不符合 24 例)。对呈 0、1+、2+ 与 3+ CLDN18 染色的肿瘤细胞比例估计,ICC 分别为 0.84、0.29、0.41 与 0.70。染色异质性病例的一致性更差(zolbetuximab 资格判定 kappa 0.49,对比非异质性 0.71)。
本研究显示消化病理医师在为 zolbetuximab 资格评估 CLDN18 染色时具有实质观察者间一致性。较弱染色强度的判读是变异较大的来源。这些发现提示,治疗决策相关的 CLDN18 染色评分需要标准化,困难病例宜采用共识判读。
- Zolbetuximab eligibility cutoff: >75% of tumor cells with 2+ or 3+ membranous staining; six GI pathologists scored digitally scanned slides from nonconsecutive (n=47) and consecutive (n=48) gastroesophageal adenocarcinoma cohorts.
- Overall H-score agreement was good (ICC 0.85 / 0.91); eligibility agreement was substantial (Fleiss kappa 0.63 / 0.72).
- Weaker staining intensities (especially 1+) and staining heterogeneity drove greater variability; standardized scoring and consensus for difficult cases are needed.
Scope: PubMed abstract only. Full text and full-text figures or tables were not collected because ScienceDirect is blocked by Cloudflare from this site’s egress. Card image from the @Human_Pathology X post.
Abstract
Gastroesophageal adenocarcinomas expressing claudin 18.2 (CLDN18) are candidates for targeted therapies such as zolbetuximab. Immunohistochemical staining for CLDN18 above a certain threshold is used to establish treatment eligibility. The purpose of this study was to evaluate the interobserver variability among pathologists in scoring CLDN18 immunostaining.
Six gastrointestinal pathologists evaluated CLDN18 staining on digitally scanned slides from a nonconsecutive cohort of 47 cases and a consecutive cohort of 48 cases of gastroesophageal adenocarcinoma. Each rater estimated the percentage of tumor cells showing 0, 1+, 2+, or 3+ membranous staining intensity (producing an overall H-score) and also noted whether they would score the carcinoma as positive according to the cutoff for zolbetuximab eligibility (>75% of tumor cells with 2+ or 3+ staining). Factors potentially influencing scoring such as heterogeneity of staining and technical or sample factors were also noted. Interobserver agreement was assessed using kappa statistics (categorical scores) and intraclass correlation coefficients (ICCs) (continuous measures).
Interobserver agreement for overall H-scores was good, with an ICC of 0.85 and 0.91 in the two cohorts. There was substantial interobserver agreement (Fleiss kappa=0.63 and 0.72 for the two cohorts) regarding eligibility for zolbetuximab therapy. For the nonconsecutive cohort, there was complete concordance among all raters in 32 cases (68%) (8 cases eligible, 24 cases ineligible). For estimated proportions of tumor cells showing 0, 1+, 2+, and 3+ CLDN18 staining, the ICCs were 0.84, 0.29, 0.41, and 0.70, respectively. Cases with heterogeneous staining also showed greater variability (kappa 0.49 vs. 0.71 for zolbetuximab eligibility).
The study demonstrated substantial interobserver agreement among gastrointestinal pathologists in evaluating CLDN18 staining for the purposes of zolbetuximab eligibility. Assessment of weaker staining intensities was a source of greater variability. These findings highlight the need for standardized scoring of CLDN18 staining for the purposes of treatment planning, ideally with a consensus approach in difficult cases.